What changed on 4 November 2026: added the earlobe CO2 laser protocols (Protocol A and B), a keloid vs hypertrophic scar diagram, a treatment-options diagram, a section on cryotherapy and five questions.
Keloid treatment in Singapore begins by confirming the lesion is a keloid rather than a hypertrophic scar, because a keloid grows beyond the original wound and tends to recur. First-line care is intralesional medical therapy, often combined with silicone, pressure, cryotherapy or laser and staged over time. Cutting a keloid out on its own is avoided.
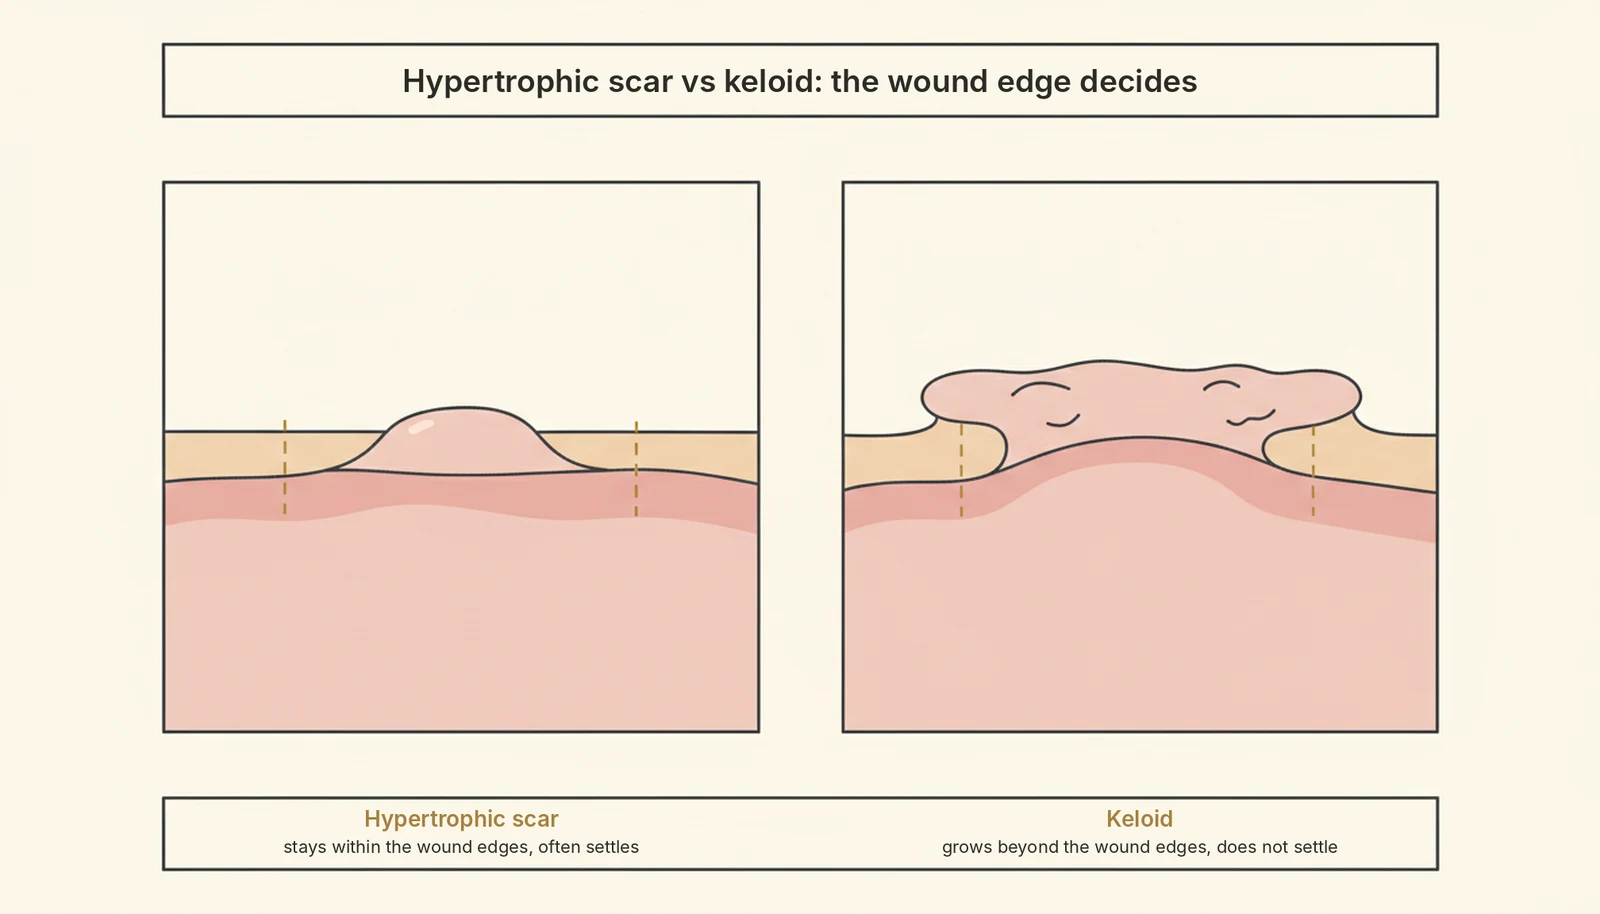
Both a keloid and a hypertrophic scar are raised. Both can itch, ache and feel tight, and to most people they look like the same problem. The difference is visible at the edge. A hypertrophic scar stays within the margins of the original wound and commonly flattens and softens with time without intervention. A keloid extends outward into skin that was never injured, and it characteristically does not regress on its own. A small piercing can produce a lesion many times the size of the original hole.
“A keloid grows past the edge of the wound that caused it. A hypertrophic scar does not. That single boundary decides almost everything that follows.”
Dr Sin YongOn distinguishing the two
Hypertrophic scar vs keloid: the wound edge decides. Diagram, not a patient. Tap to enlarge.
Why it keeps growing
Normal wound healing has a remodelling phase: collagen laid down during repair is reorganised and the scar settles back toward the level of the surrounding skin. In a keloid, that phase does not conclude. Deposition of type I and type III collagen continues well past the point where healing should have finished, and the lesion expands. Genetic susceptibility is a major factor, which is why keloids frequently run in families, and why a family history is worth mentioning at consultation even if you have never formed one yourself.
More common in Singapore than elsewhere
Keloid formation is substantially more common in people of Chinese, Malay, Indian and African descent than in those with white European skin, so in Singapore it is a routine presentation. Common sites follow skin tension: earlobes after piercing, the upper chest, the shoulders, the upper back and along the jawline. Keloids also arise on surgical scars, burns, acne lesions and sometimes vaccination sites, which is where this overlaps with acne scar treatment, though the two are managed differently.
Keloids are not only a cosmetic concern. Itch, tenderness, a burning or stinging sensation, and restriction of movement where a keloid crosses a joint or the neck are common, and for many patients those symptoms are the reason they seek assessment.
Illustrative image, not a patient.
Who keloid treatment suits, and who should wait
Treatment suits a raised scar that has grown past the original wound edge, especially one that itches, aches or feels tight, in someone who can attend staged reviews and accepts that keloids tend to recur.
Who it suits, who should wait, who is referred on
Group
Typical situation
What usually happens
Tends to suit
A keloid on the earlobe, chest, shoulder or jawline with itch, tenderness or tightness; willing to attend staged reviews
Staged intralesional therapy with adjuncts chosen by site
Better to wait
Pregnancy or breastfeeding; active infection or inflamed skin over the lesion; freshly tanned skin where laser is planned
Choice of medicine reviewed; treatment deferred until the skin is ready
Caution
Known allergy to the planned medicine or local anaesthetic; bleeding disorder or blood-thinning medicines; conditions that affect injectable medicines
Declared and discussed before any course begins
Examined first
A lump that appeared without injury, grows quickly, bleeds, ulcerates or looks different from your other scars
Medical review to confirm the diagnosis; a biopsy is occasionally needed
Referred on
Large keloids not responding to non-surgical care
Plastic surgery specialist, with adjuvant treatment afterwards
Plan ahead
A personal or family history of keloids before a piercing or elective procedure
Risk discussed and the procedure planned accordingly
People who expect a keloid to be cut out and gone in one visit, or who cannot attend ongoing review, tend to respond poorly, because keloids are managed over time.
Keloid treatment options compared: which route, and where
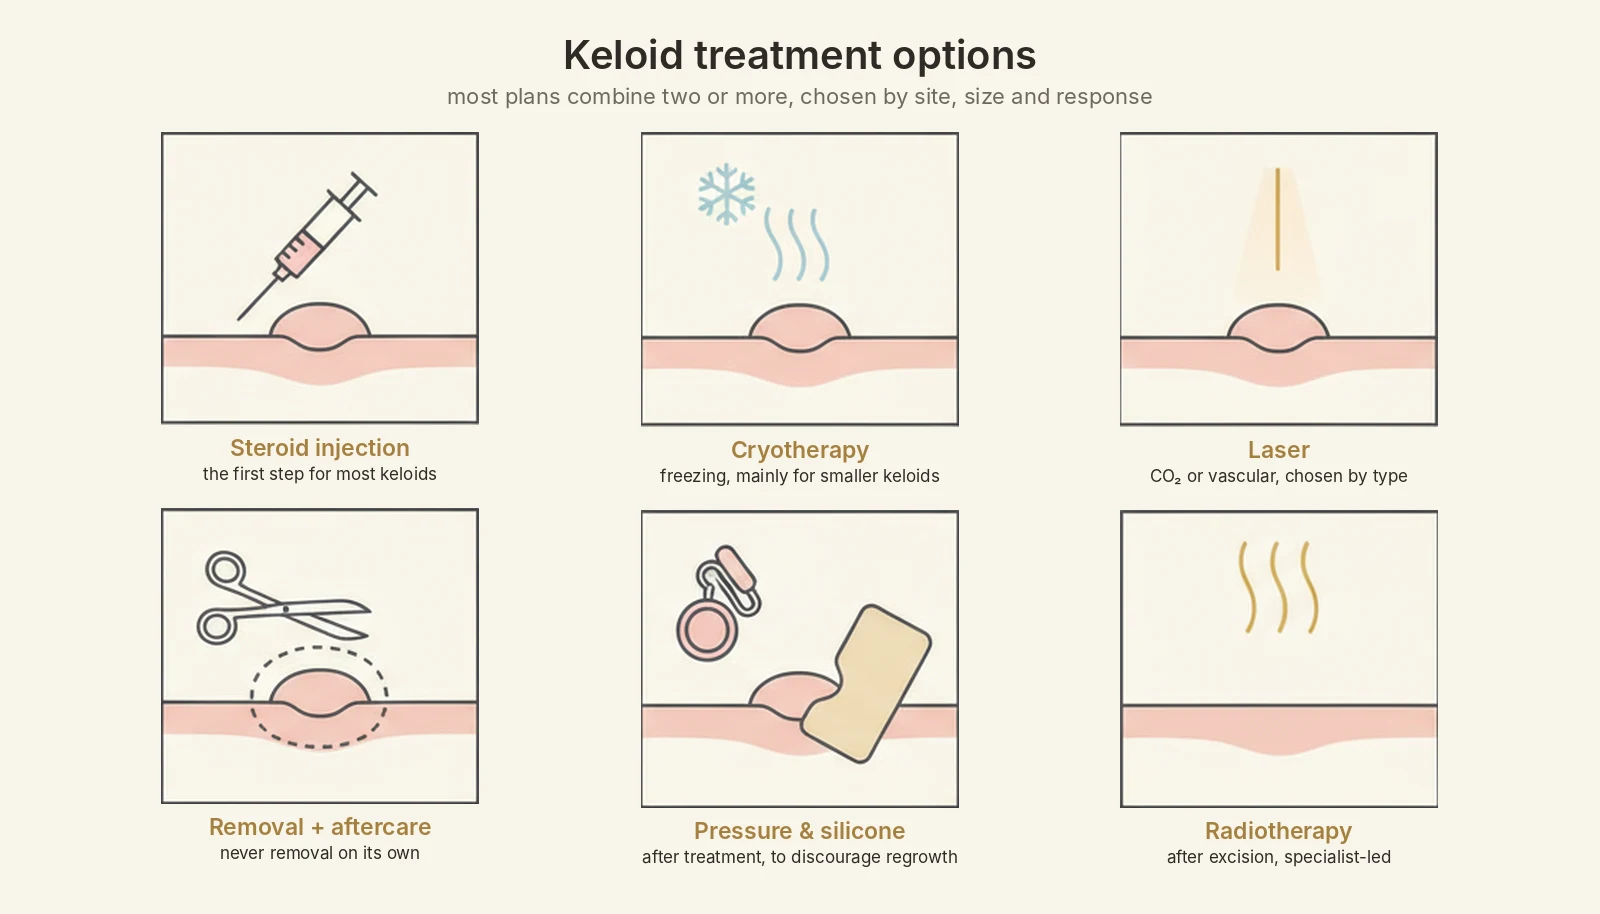
Intralesional medical therapy is first-line, usually a corticosteroid, sometimes combined with another medicine such as 5-fluorouracil. Adjuncts are selected by site, by how old the lesion is, and by how it has responded to anything tried before. Plans are usually combined rather than single-modality, and staged over time rather than completed in one visit. The international scar recommendations and the Japanese keloid guidelines listed under References describe the same principle.
The main keloid treatment options. Most plans combine two or more. Diagram, not a patient. Tap to enlarge.
Medicine placed into the keloid to soften and flatten it and settle itch and tenderness; sometimes combined with 5-fluorouracil
Remove the underlying tendency to form keloids, or prevent recurrence on its own
Most keloids, as the first step, often alongside an adjunct
Silicone gel or sheeting
Hydrates and covers the scar surface to help soften and flatten raised scar tissue
Reduce a large, established keloid by itself; it needs consistent daily use
Small or early lesions, fresh surgical scars in keloid-prone skin, and maintenance
Pressure therapy
Sustained pressure on the scar, for example pressure earrings after an earlobe keloid is treated
Work where even pressure cannot be applied
Earlobe keloids, particularly after treatment
Cryotherapy
Freezes the lesion to reduce its bulk, sometimes combined with intralesional therapy
Avoid lightening of the treated skin, which is more noticeable in darker skin
Smaller keloids at sites where freezing is practical
Laser
Targets the redness and surface texture of the scar, as an adjunct
Flatten a bulky keloid on its own or replace injection
Red or textured keloids on the chest, shoulders and jawline
Surgical excision with adjuvant treatment (CO2 laser removal for earlobe keloids; other sites referred to a plastic surgery specialist)
Removes the bulk, followed by intralesional therapy, silicone or pressure to suppress regrowth
Be relied on alone, or used under high skin tension
Selected earlobe keloids and lesions that have not responded to staged medical treatment
Cryotherapy for keloids in Singapore
Cryotherapy freezes keloid tissue from the surface or from within, and is used mainly for smaller keloids, often alongside steroid injection so the two work together. Its main drawback is lightening of the treated skin, which shows more in darker skin types, so it is chosen carefully on the face, jaw and neck. It is one option within a plan rather than a treatment on its own.
Keloid removal in Singapore: what changes by body site
Skin tension, how pressure can be applied and how visible lightening would be differ across the body, so the site changes the plan.
Keloid treatment by body site
Site
Why it behaves this way
What tends to be considered
What is avoided
Earlobe after piercing
Low tension, and the lobe can be compressed
Intralesional therapy; CO2 laser removal with steroid and a pressure earring for bulky keloids, or fractional CO2 with steroid delivery for flatter ones (see Protocol A and B)
Excision alone, or re-piercing before review
Chest and upper back
High skin tension, acne as a common trigger, spreading shapes
Intralesional therapy with silicone; laser for redness
Cutting out under tension
Shoulders
Tension and constant movement
Intralesional therapy with silicone and adjuncts chosen by the age of the lesion
Surgery as the first step
Jawline and neck
Acne, shaving and movement
Intralesional therapy, with silicone or laser for redness
Cryotherapy where lightening would be visible in darker skin
Surgical scars
A fresh wound in keloid-prone skin
Silicone and close review while healing; intralesional therapy if it grows past the wound edge
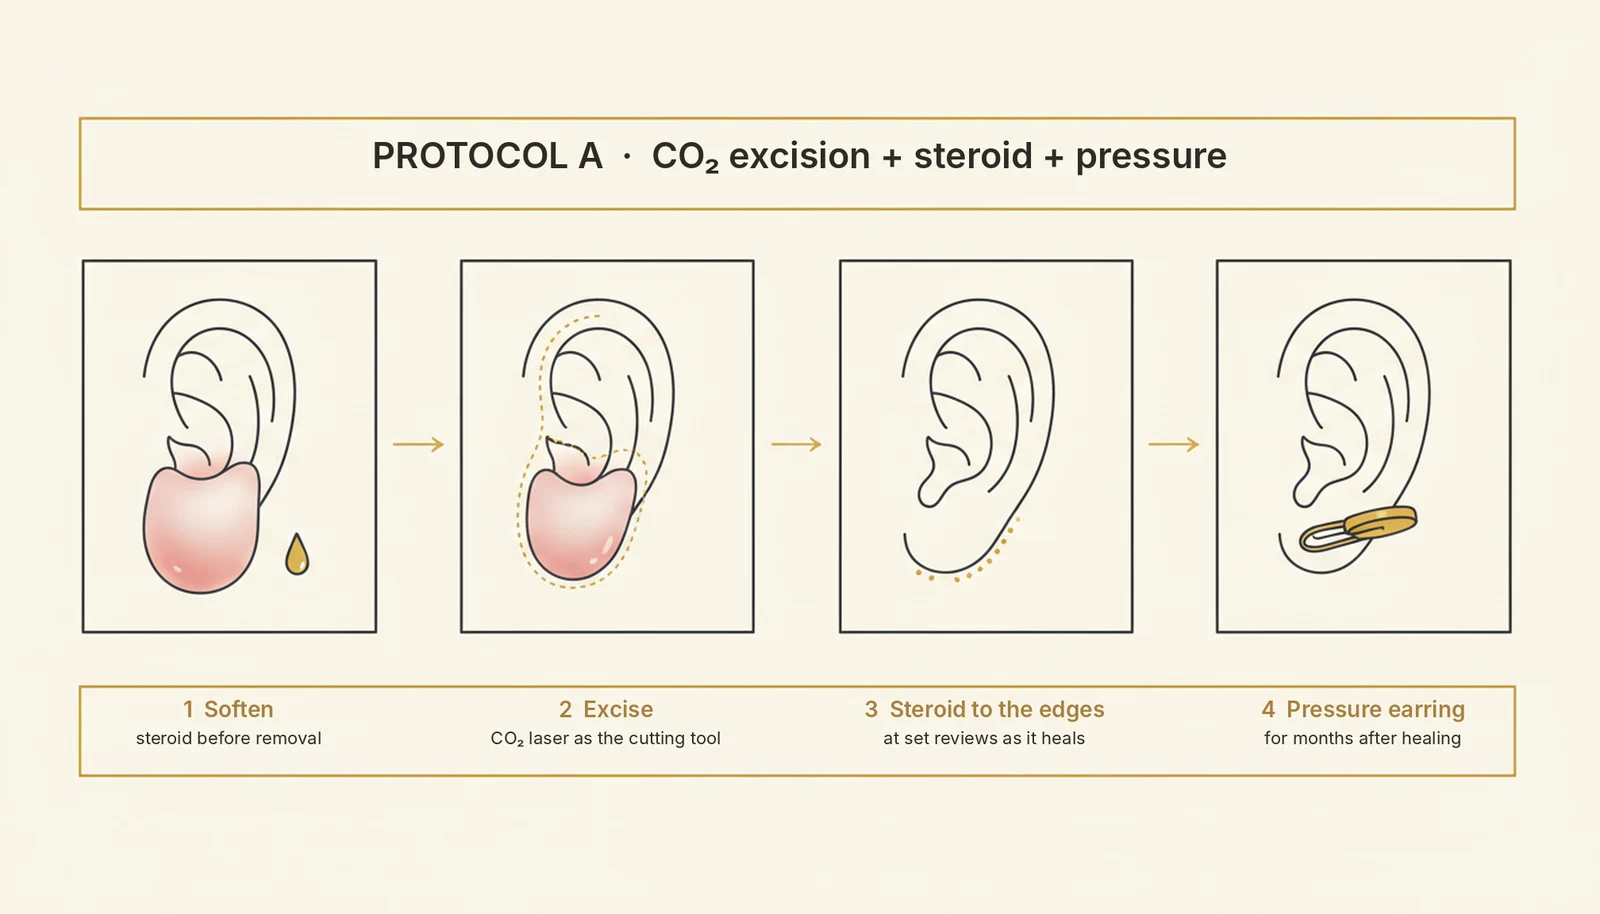
Earlobe keloid, Protocol A. Diagram, not a patient. Tap to enlarge.
What keloid treatment cannot do: why cutting it out is not the answer
It is the first thing most people ask, and it deserves a direct answer. A keloid is an abnormal, prolonged wound-healing response in skin that is prone to it. Cutting it out creates a fresh wound in that same skin, so excision alone carries a high recurrence rate, and the keloid that comes back is frequently larger than the one removed. Where surgery has a role at all, it is combined with adjuvant treatment rather than performed on its own.
Treatment does not remove the underlying tendency to form keloids.
Laser does not flatten a bulky keloid by itself, and silicone does not reduce a large, established one alone.
No plan can promise that a keloid will not return.
A raised scar that stays within its wound edge is a hypertrophic scar, which is managed differently; see keloids and hypertrophic scars.
The part that is said upfront
Keloids have a genuine tendency to recur, and any honest conversation includes that from the beginning. Treatment is directed at flattening, softening and controlling symptoms: the itch, the tenderness, the tightness across a joint or the neck. Response varies with the size, site and age of the lesion, skin type, genetic factors and previous treatment, and ongoing review is frequently part of the plan.
Two myths we hear in clinic
“A keloid can simply be cut out.”
Excision alone frequently recurs, often larger, because the cut is a fresh wound in skin prone to abnormal healing.
“A keloid and a hypertrophic scar are the same.”
A keloid grows beyond the wound edge and does not regress on its own, while a hypertrophic scar stays within it and often flattens.
Risks and side effects of keloid treatment
Expected effects include local tenderness, swelling, redness and bruising at the treated site and, with cryotherapy, blistering and crusting that heal over time. Injections into a keloid are uncomfortable because the scar tissue is dense, and cryotherapy stings while the area is frozen. Less commonly there can be thinning or lightening of the nearby skin, which is more noticeable in darker skin, or transient redness after laser. A keloid can also return despite treatment, which is why review is built into the plan. Risks are explained before a course begins.
Contact the clinic the same day if
Pain increases, or redness spreads, with pus or fever
Declare all medicines and medical conditions, especially blood thinners and any condition that affects injectable medicines.
Tell Dr Sin Yong about any family history of keloids and the piercing, acne or procedure that triggered yours.
Avoid fresh sun exposure on the area, and say if you are pregnant, planning pregnancy or breastfeeding.
Bring records of earlier injections, surgery or laser on the scar, and your own photos showing how it has changed.
On the day
Consultation and examination: Dr Sin Yong confirms whether it is a keloid and checks site, size and history.
A written plan and quote naming the combination of treatments and how they are staged.
Treatment: the chosen approach is delivered at the site, with comfort measures and clear instructions.
Review and adjustment: the lesion is reviewed over time and the plan adjusted to how it responded.
Aftercare
Keep the area clean and dry as instructed, and avoid picking or scratching.
Avoid tight clothing or jewellery over the site unless advised.
Use silicone or pressure as prescribed, and a bland moisturiser around, not on, any crusting or blistered skin.
Protect the treated area from the sun, as treated skin can change colour, and avoid scrubs and irritating products on the scar.
Attend the review so the response can be checked.
Keloid removal in Singapore: what decides the price
Keloids vary widely between patients, so cost follows the plan rather than a fixed list. It depends on the size and number of lesions, since a single earlobe keloid differs considerably from extensive chest involvement; the site, because skin tension and accessibility affect what is appropriate; which modalities the assessment indicates, since most plans combine more than one; the medicines and consumables involved; and how the plan is staged with review. A written quote is given at consultation after assessment, and the consultation also decides whether treatment is advised at all. How quotes work at this practice is explained on how we quote.
How Dr Sin Yong approaches keloids
Keloids are managed medically first, so an aesthetic physician or dermatologist experienced with scars is a reasonable place to start. Dr Sin Yong first confirms that the lesion is a keloid rather than a hypertrophic scar, by looking at whether it has grown past the edge of the wound. He asks about family history and the trigger, such as a piercing, acne or surgery, and examines any lump that does not look like a typical keloid before treating it as one.
Intralesional medical therapy is first-line, and silicone, pressure, cryotherapy or laser are added according to the site, the age of the lesion and how it responded before. In darker skin, cryotherapy is avoided where lightening would be visible. Plans are staged with review rather than finished in one visit, and the recurrence risk is stated at the start. For a bulky earlobe keloid, Dr Sin Yong removes it with the CO2 laser and follows with steroid to the healing edges and a pressure earring (Protocol A); excision at other sites, where it is appropriate, is referred to a plastic surgery specialist and combined with adjuvant treatment, and radiotherapy after excision is decided by a specialist team.
Related on this site
Acne on the chest and shoulders is a common trigger for raised scars; see the guide to bacne.
For how back acne scars are sequenced after active disease, see the back acne page.
Keloid treatment: questions patients ask
A keloid grows beyond the edge of the original wound into skin that was never injured, while a hypertrophic scar stays within the wound margins. A hypertrophic scar often flattens and softens with time; a keloid characteristically does not regress on its own and tends to recur after cutting. The distinction decides the plan, so it is confirmed at examination before keloid treatment starts.
A keloid should be checked by a doctor when it is growing, itching or painful, when it follows a piercing or acne on the chest or shoulders, or before any attempt to cut or freeze it. A raised lump that bleeds, breaks down or does not look like a typical keloid is examined as a lump in its own right before it is treated as a scar.
Surgery alone is the approach most likely to regrow a keloid, often larger, because the cut is a fresh wound in keloid-prone skin. Where excision has a role, it is for selected lesions and is always followed by adjuvant treatment such as intralesional therapy, silicone or pressure: on the earlobe it is done here with the CO2 laser (Protocol A), and at other sites by referral to a plastic surgery specialist. Most keloids are treated with staged intralesional therapy and adjuncts instead.
Intralesional corticosteroid injection is first-line, sometimes combined with another medicine such as 5-fluorouracil. Silicone, pressure, cryotherapy and laser are added according to the site, the age of the lesion and how it has responded before. Plans are staged and reviewed rather than completed in one visit, and recurrence is discussed from the outset.
Keloids characteristically do not flatten on their own, which is one way they differ from hypertrophic scars, which often settle with time. A keloid may stop growing, but it usually stays raised and can keep itching. If a raised scar is still changing, it is worth having it examined, because earlier treatment is generally easier to plan than treatment of a large, established keloid.
Keloids have a genuine tendency to recur, and any honest discussion includes that. Treatment aims at flattening, softening and symptom control rather than a promise that the keloid will not return. Ongoing review is often part of the plan, and that is discussed openly at consultation rather than after.
Not always, but the risk can be reduced. If you or a close relative has formed keloids, avoid elective piercings and unnecessary skin injury, treat acne early, and mention the history before any procedure that breaks the skin. After surgery, early silicone and review while the wound heals help catch a scar that starts to spread past its edge.
An earlobe keloid can often be flattened with intralesional therapy, and pressure earrings help after treatment. A bulky earlobe keloid can be removed with the CO2 laser (Protocol A), always combined with steroid to the healing edges and a pressure earring, because removal alone tends to recur. Re-piercing is not discussed until the ear has been reviewed, since the same ear can form another keloid.
Not on its own. Laser is used as an adjunct: it can reduce the redness of an active keloid and improve surface texture, but it does not flatten a bulky lesion by itself. It is usually combined with intralesional medical therapy and other measures chosen for the site and the age of the keloid.
The cost of keloid treatment in Singapore depends on the size and number of lesions, the site, the modalities the assessment indicates, the medicines and consumables involved, and how the plan is staged with review. A written quote is given at consultation, after Dr Sin Yong has examined the scar. The consultation also decides whether treatment is advised, so no figure is given in advance.
A piercing bump is usually a small, soft, red or skin-coloured swelling right at the hole, often from irritation or infection, and it tends to settle once the cause is treated. A keloid is firm, keeps growing beyond the hole, often months later, and does not go away on its own. A lump that is still growing after a few weeks should be examined.
A keloid can be removed or flattened, but the tendency to form keloids stays in the skin, so recurrence is always possible. The chance of regrowth is lowered by combining removal with steroid, pressure or other adjuvant treatment and by keeping follow-up reviews. No treatment can promise a keloid will never return.
There is no single best treatment. Steroid injection into the keloid is usually the first step, and silicone, pressure, cryotherapy, laser or removal are added depending on where the keloid is, how big and how old it is, and how it has responded before. Most keloids need a combined, staged plan.
Steroid injections sting briefly, and numbing cream or local anaesthetic is used where needed. Removing an earlobe keloid with the CO2 laser is done under a local anaesthetic nerve block, so the removal itself should not be painful, though the area can feel sore for a few days afterwards.
Cryotherapy freezes keloid tissue and can help flatten smaller keloids, often alongside steroid injection. It can leave lighter patches, which show more in darker skin, so it is used selectively, and less often on the face, jaw and neck where lightening would be visible.
The keloid removal Singapore price depends on the size and number of keloids, whether injection, laser or excision with aftercare is planned, and how many staged visits the keloid needs. Dr Sin Yong examines the keloid first and gives the fee in writing rather than quoting a flat figure.
Keloid. StatPearls. National Center for Biotechnology Information. source
The Most Current Algorithms for the Treatment and Prevention of Hypertrophic Scars and Keloids: A 2020 Update of the Algorithms Published 10 Years Ago (Ogawa R). Plastic and Reconstructive Surgery, 2022. pubmed.ncbi.nlm.nih.gov
Diagnosis and Treatment of Keloids and Hypertrophic Scars: Japan Scar Workshop Consensus Document 2018 (Ogawa R, Akita S, Akaishi S, et al.). Burns & Trauma, 2019. pubmed.ncbi.nlm.nih.gov
International clinical recommendations on scar management (Mustoe TA, Cooter RD, Gold MH, et al.). Plastic and Reconstructive Surgery, 2002. pubmed.ncbi.nlm.nih.gov
Keloids and Hypertrophic Scars: Pathophysiology, Classification, and Treatment (Berman B, Maderal A, Raphael B). Dermatologic Surgery, 2017. pubmed.ncbi.nlm.nih.gov
Where Dr Sin Yong consults: Orchard Road, Singapore (unit on booking) · Orchard MRT · Mon–Fri 10am–8pm, Sat 11am–3pm · WhatsApp +65 8023 7170 · Getting here · How fees are quoted