Back acne treatment Singapore: the first step is diagnosis, because true acne and Malassezia (fungal) folliculitis look almost identical across the back, chest and shoulders and need different medicines. Dr Sin Yong examines the eruption, then plans washes, topical or oral medicines and, where marks remain, laser for the red or brown marks and the scars.
Main guideAcne treatment Singapore — what it treats, who it suits, sessions, downtime and what decides the cost, by Dr Sin Yong.
Dr Sin Yong · MBBS (NUS) · MRCS (Edin) · MSc Aesthetic Medicine with Distinction (Queen Mary, London) · MSc Practical Dermatology (Cardiff) · Global Key Opinion Leader
Half the battle with “bacne” is the diagnosis. True acne and Malassezia folliculitis, a yeast-driven condition, look almost identical across the back, chest and shoulders, and treating one with the other’s medication fails month after month. The examination settles it first, and the plan follows the diagnosis.
Body acne treatment in Singapore: what about back acne scars?
Active back and body acne is treated first, with body washes, prescription medicines and R2 laser, because new spots keep scarring. Back acne scars and dark marks are then treated with laser or RF microneedling once the skin is calm; raised scars on the chest and back should be reviewed early.
How many sessions does back acne treatment need?
Medicine-based treatment for back acne is reviewed every four to eight weeks, and most people see clear improvement over two to three months. If laser is added for active acne or marks, sessions are usually spaced three to four weeks apart; the number depends on severity.
Invited by Device Makers to Share His Expertise
Global Key Opinion Leader for 14+ device brandsShared his clinical expertise with 500+ doctors across AsiaMBBS (NUS) · MRCS (Edinburgh) · MSc with Distinction (Queen Mary, London) · MSc (Cardiff)Every treatment personally performed — never delegated
Back acne treatment in Singapore starts with diagnosis, because true acne and fungal (Malassezia) folliculitis look alike on the back and chest but need different medicines. Active bacne is cleared first with treatment matched to cause and severity, and marks or scars are treated once the skin is quiet. Dr Sin Yong assesses and treats this personally at his clinic on Orchard Road, Singapore.
Diagnosis first: true acne and fungal folliculitis look alike on the back and chest but need different medicines.
Clear active acne: washes, topical retinoids and oral medicines, including isotretinoin for severe or scarring acne, are matched to the diagnosis and grade.
Reduce the triggers: sweat, friction and occlusion from gym wear, bags and humidity keep follicles inflamed.
Then marks and scars: treated once breakouts are quiet, with the scar type deciding the tool.
Raised scars: the chest and shoulders are keloid-prone, which is weighed before any scar procedure.
What is back acne, and how does treatment work?
True back acne (bacne, sometimes spelled backne) is acne vulgaris on the trunk: a disease of the oil gland and the hair follicle, with blocked pores (comedones) at its root. The back, chest and shoulders carry dense sebaceous glands under thicker skin, and in Singapore that skin is wrapped in sweat, friction and occlusion from gym wear, backpacks and humidity. Breakouts here run deeper and scar more readily than facial acne, and the marks they leave fade more slowly. Over-the-counter washes rinse the surface, but the biology is happening in the follicle.
Hormones play a part wherever acne appears, because androgens drive sebum production in the glands of the back and chest. Body acne that flares with the menstrual cycle, starts suddenly in adulthood, or comes with irregular periods or excess hair growth may prompt a hormonal assessment. Anabolic steroids and some supplements can also trigger body acne, so it helps to mention them.
Diagnose, clear, then repair
Treatment runs in stages: confirm what the eruption actually is; clear active disease with medical treatment matched to that diagnosis; address the sweat, occlusion and friction that keep follicles inflamed; and only then treat what is left behind. Skipping stage one is why so many bacne plans fail. Skipping stage two is how scars are made.
What back and body acne treatment addresses
Active back and chest acne, from comedones to deeper nodules, managed medically by severity.
Fungal folliculitis, treated as the separate condition it is.
True scars, including the chest and shoulders' tendency to thickened scarring, assessed alongside keloid treatment where relevant.
Active acne is treated before scars are addressed. Illustrative image, not a patient.
Bacne, fungal folliculitis or something else? Telling them apart
The word bacne covers several different eruptions, and back acne treatment in Singapore works when it is matched to the right one. True acne is a disease of the oil gland and follicle. Bacterial folliculitis is an infection of the hair follicle, usually by Staphylococcus, that follows shaving, friction, occlusion or a hot tub. Malassezia folliculitis is a yeast overgrowth in the follicle that thrives on sweat and heat and is aggravated by acne antibiotics. Two other conditions are often mistaken for back acne: keratosis pilaris and hidradenitis suppurativa.
Gentle cleansing is advised in the first days after skin treatments. Illustrative image, not a patient.
Back and body bumps compared: what each looks like and what it needs
Condition
What it looks like
What drives it
What it needs
Acne vulgaris (true back acne)
Mixed lesions of different sizes and stages: blackheads, whiteheads, papules, pustules and the occasional deep nodule, with old marks beside new spots
Oil production, follicular blockage and inflammation, often with facial acne alongside
Medical treatment matched to severity; marks and scars afterwards. See acne treatment
Bacterial folliculitis
Tender red pustules centred on hairs, often in a crop after a trigger
Staphylococcus entering follicles after shaving, waxing, tight clothing, friction or a hot tub
Removing the trigger, antiseptic washes and, where needed, antibacterial treatment chosen after examination; a swab if it recurs
Malassezia (fungal) folliculitis
Uniform, itchy, same-size small bumps across the shoulders, upper back and chest, flaring after sweating
Yeast overgrowth in warm, occluded follicles; worse after oral antibiotics or steroids
Antifungal treatment; antibacterial acne treatment does not help. See fungal acne
Keratosis pilaris
Rough follicular bumps from keratin plugs; not acne and not infected
Keratin build-up in the follicle opening, usually on the upper arms and thighs
Deep, painful, recurrent nodules, sometimes with tunnels, in the armpits, groin and under the breasts
A different, deeper inflammatory condition
Referral for dermatology assessment
Telling them apart starts with the lesions. Comedones mean acne; folliculitis of either kind has none. A tender crop of pustules around hairs after a new razor, a tight strap or a hot tub points to a bacterial cause. Monomorphic itchy bumps in a humid climate point to yeast, and a history of worsening on an acne antibiotic almost settles it. Where the picture is unclear, a simple swab or a skin scraping at the consultation decides, and more than one eruption can be present on the same back at once.
Bacne and body acne treatment: what changes away from the face
Body acne is treated on the same principles as facial acne, grading it and confirming that it is acne, but the back, chest and shoulders change the practical plan. Confirming the diagnosis matters more here than on the face, because Malassezia folliculitis is commonest on the trunk: uniform, itchy bumps of similar size that do not respond to acne treatment and can worsen with antibiotics.
Surface area is the next consideration. Leave-on creams are hard to apply evenly across the back, so wash-off formulations such as benzoyl peroxide washes are often used, with the caveat that benzoyl peroxide bleaches towels and fabric. Where body acne is widespread, inflamed or nodular, oral treatment tends to be considered earlier than it would be for a few facial spots, and the options and their monitoring are the same as for facial acne.
Sweat, heat and friction aggravate it. In Singapore's humidity, tight synthetic sportswear, backpack straps and staying in damp clothes after exercise all add occlusion; changing promptly and choosing looser fabrics help. Post-inflammatory marks on the trunk often outlast the spots, and laser directed at the inflammatory component may be added alongside medical management, as on the face.
Who does back acne treatment suit, and who should wait?
Most people with persistent breakouts on the back or chest are suitable for an assessment. What differs is which medicines are appropriate and when.
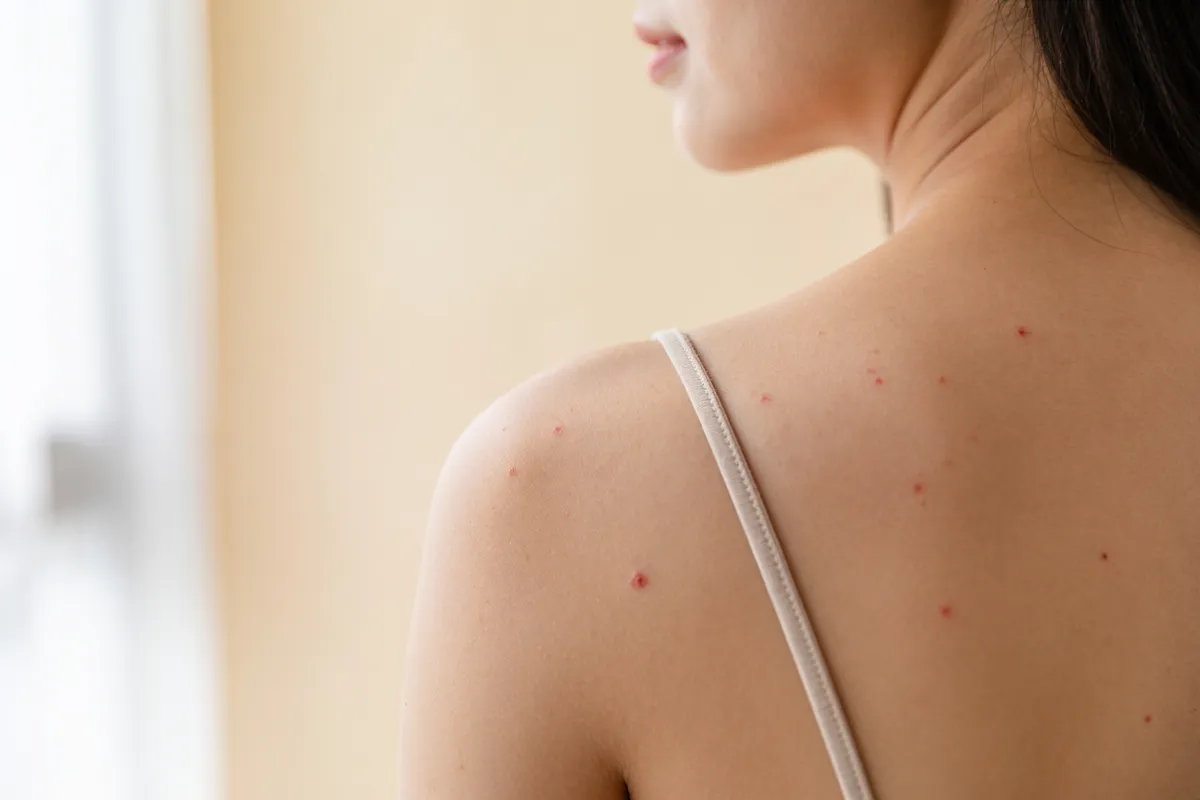
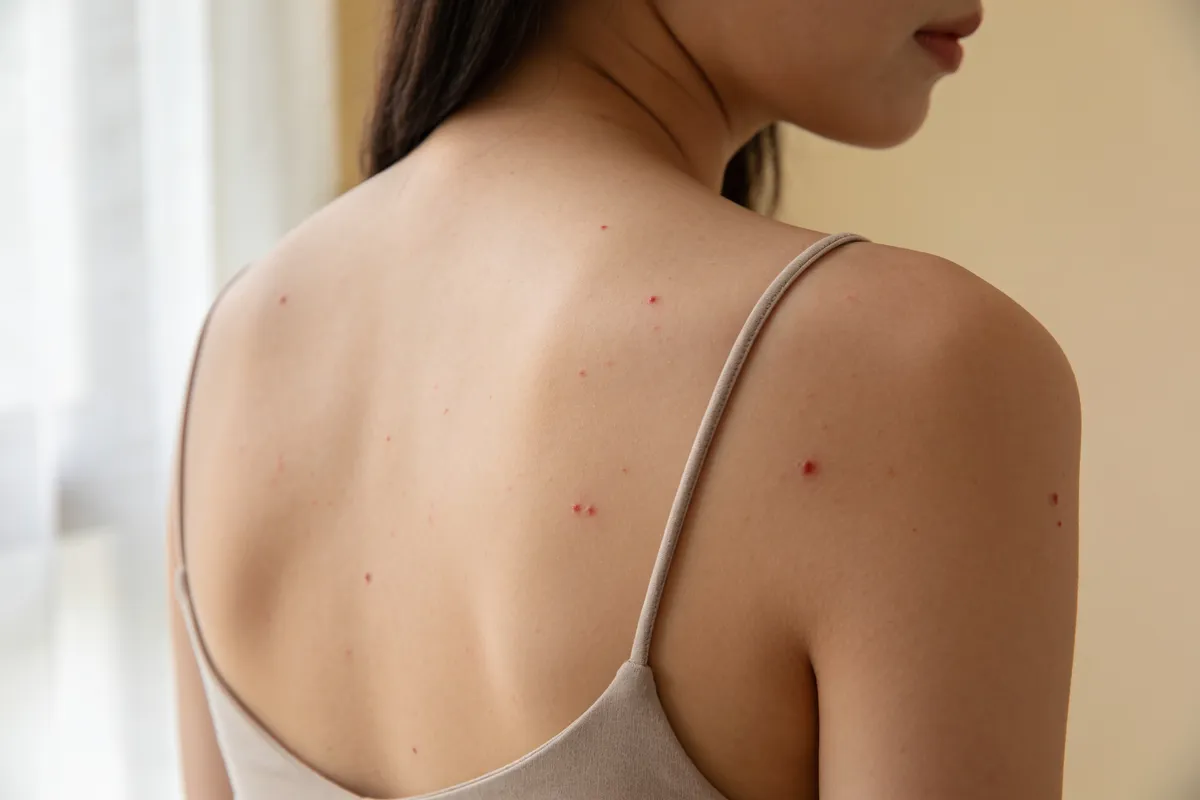
Back acne is assessed by the type of blemish. Illustrative image, not a patient.
Who it suits, who should wait, who is referred on
Group
Typical situation
What usually happens
Tends to suit
Persistent comedones, papules, pustules or nodules on the back or chest; itchy uniform bumps that flare with sweat; breakouts that recur despite over-the-counter washes
Examination, diagnosis and a medical plan matched to the eruption
Marks or scars
Brown or red marks, or true scars, once active disease is quiet
Assessed on their own merits after clearance, with the scar type deciding the tool
Better to wait
Pregnancy or planned pregnancy; recent isotretinoin before any resurfacing or laser; active infection or open lesions where laser or energy treatment is planned
Medicines chosen to suit the situation; procedures deferred until it is appropriate
Some medicines unsuitable
Known allergy to a prescribed medicine or ingredient; liver or other conditions that limit particular oral medicines
Alternatives discussed at the consultation
Keloid tendency
Personal or family history of thickened scars, especially on the chest and shoulders
Weighed before any scar procedure
Referred on
Severe, scarring or treatment-resistant disease; lesions of uncertain diagnosis; suspected hidradenitis suppurativa
Referral for dermatology review
People who expect one product or a single visit to end breakouts, or who will not adjust sweat and clothing triggers, tend to respond poorly.
Back acne treatments compared: which option for which eruption
There is no single back acne treatment. The choice follows the diagnosis first and the severity second, and active disease is always cleared before marks and scars are addressed. Prescription options are discussed only after examination.
Back and body acne treatments compared
Option
What it does
What it cannot do
Who it tends to suit
Benzoyl peroxide wash and topical retinoids
Act on acne bacteria and follicular blockage in milder body acne
Treat fungal folliculitis, or deep nodules on their own
Mild comedonal and inflammatory back and chest acne
Oral antibiotics such as doxycycline (prescription-only)
Reduce inflammatory papules and pustules over a defined course
Treat a yeast-driven eruption, which antibiotics can aggravate
Acts on sebum production and the acne process itself
Be taken in pregnancy; it requires monitoring
Severe, nodular or scarring body acne
Antifungal treatment (topical or oral)
Acts on Malassezia yeast in the follicle
Treat comedonal acne
The uniform, itchy bumps of fungal folliculitis
Scar and mark treatment: subcision, resurfacing, Secret DUO, FSX Laser or S3 Resurfacing Lift
Addresses post-inflammatory marks and true scars once disease is quiet; subcision for tethered scars, resurfacing for texture, Secret DUO where the surface should be spared
Back, chest and shoulders: each zone is planned differently
The back carries dense sebaceous glands under thicker skin, and the upper back also collects residue from hair conditioner running down it. The chest meets sweat, heavy body butters and occlusion. The shoulders and strap lines meet friction from bags and gym wear, and the deeper nodules there are the ones most likely to scar. The chest and shoulders are also keloid-prone zones, so the tendency to thickened scarring is weighed before any scar procedure. A body-specific plan is needed because concentration, vehicle and the area covered all differ from facial care.
Back acne scar treatment in Singapore: marks and scars by type
Back acne scar treatment in Singapore starts once breakouts on the back, chest and shoulders are under control, because new scars keep forming behind active acne. What is left is then sorted by type, since flat marks, depressed scars and raised scars on the trunk each need a different tool, and the back heals more slowly than the face.
The back is harder to reach and to treat at home. Illustrative image, not a patient.
Mark or scar
How it looks on the back
What is used
Why the back differs
Brown marks (post-inflammatory hyperpigmentation)
Flat brown patches where spots have settled
Sun protection, topical care and pigment-directed laser once acne is quiet
Marks on the trunk fade more slowly than on the face; resurfacing can darken them
Red marks (post-inflammatory erythema)
Flat pink or red marks that fade when pressed
Acne control, then FSX Laser or vascular settings
Friction from straps and clothing can keep them inflamed
Depressed scars
Rolling dips and boxcar dents, often across the upper back
Subcision for tethered scars; Secret DUO RF microneedling where the surface should be spared; FSX Laser or the S3 Resurfacing Lift by depth
Settings are more conservative and stages more widely spaced, because back skin heals slowly
Hypertrophic scars
Raised, firm scars that stay within the original spot
Injection-based care and silicone
Skin tension on the trunk favours thickened scars
Keloids
Raised scars that spread beyond the original spot, common on the chest and shoulders
Steroid injection first, with silicone or laser for redness
Not cut out under tension, because excision alone tends to recur
A 2023 review of truncal acne and scarring notes that studies of the trunk are limited and that treatment guidelines are largely derived from facial protocols (Daniele 2023), which is why settings are adapted to back skin rather than copied from the face. Depressed scars follow the scar-by-scar logic on acne scar treatment, and raised scars the path on keloid treatment.
Does back acne treatment work? What the trials cover
Few acne trials have studied the back specifically. A review of trifarotene, a topical retinoid, describes it as the first with rigorous clinical trial data on both safety and efficacy in truncal acne, from large randomised controlled trials. A broader 2023 review concludes that studies of truncal acne remain limited and that guidance is largely derived from facial protocols.
Gentle cleansing twice a day is enough; scrubbing worsens acne. Illustrative image, not a patient.
The same review also covers scarring on the trunk and calls truncal acne an understudied clinical problem. This supports controlling active acne first and assessing scars afterwards. Prescription treatment is given only after a medical consultation.
What back acne treatment cannot do, and the alternatives
It cannot work on the wrong diagnosis. Uniform itchy bumps across the shoulders are often Malassezia folliculitis, which worsens with acne antibiotics and needs antifungal treatment instead.
It is not a body-wash problem. Washes alone rarely settle deep follicular disease; the plan is medical and matched to the cause.
Laser does not clear active acne. Lasers and other energy-based tools are used afterwards, for the marks and scars that body acne leaves.
Scars are not treated first. Scar treatment during active breakouts wastes effort, because new scars are still forming behind it.
It cannot promise you will never have another breakout. Acne can recur when treatment stops, and how long the skin stays clear depends on the diagnosis, hormones, sweat, clothing and maintenance.
Some bumps are not acne at all. Keratosis pilaris and hidradenitis suppurativa need their own plans, and the second is referred on.
Two myths we hear in clinic
“Back acne is just ordinary acne and any acne product will treat it.”
Some back breakouts are Malassezia folliculitis, which does not respond to antibacterial acne treatment.
“Scrubbing harder or washing more often clears body acne.”
Friction and over-washing irritate inflamed follicles, and the underlying problem sits in the follicle, not on the surface.
What are the risks and side effects of back acne treatment?
Expected effects of medical treatment include dryness, irritation and bleached fabric from benzoyl peroxide. Oral medicines bring their own effects, such as sun sensitivity or digestive upset, which are explained before they are prescribed. Prescription-only medicines such as isotretinoin need monitoring and strict pregnancy prevention. Less often there can be allergic reactions, or a flare before the skin settles. Laser treatment of marks or scars is considered only once disease is quiet, and carries its own risks of redness and pigment change.
Contact the clinic the same day if
Redness, pain or pus spreads quickly
You have a fever or feel unwell with a skin flare
A rash, swelling or itching starts after a new medicine
You notice mood changes or severe headaches on oral treatment
What should you expect? Before, at the consultation and aftercare
Back acne is assessed by the type of blemish. Illustrative image, not a patient.
Before you book
List all medicines and supplements, including past isotretinoin or antibiotics.
Tell the clinic if you are pregnant, breastfeeding or planning pregnancy.
Avoid sun exposure and tanning on the area before the visit.
Bring the products and washes you use on your back and chest, and photos of past flares or earlier treatment records.
At the consultation
Examination and diagnosis: the eruption is characterised as acne, folliculitis or both, and severity is graded across the affected zones.
A written plan and quote: medical treatment matched to the diagnosis is set out, from topical regimes to oral therapy where indicated.
Habit and trigger review: sweat, fabrics, training routines and skincare are adjusted alongside the medicines.
Review and adjustment: the response is reviewed, and marks or scars are assessed once disease is quiet.
Aftercare and a shower routine
Apply prescribed treatments exactly as directed and avoid scrubbing or picking. Shower soon after exercise or a hot commute rather than letting sweat dry on the skin. Wash your hair and rinse out conditioner first, then wash the body, so residue does not sit on the upper back. If a medicated wash such as benzoyl peroxide or an antifungal wash has been advised, leave it on for the contact time you were given before rinsing. Benzoyl peroxide bleaches fabric, so white towels and old shirts help. Pat the skin dry, use a light non-comedogenic moisturiser if treatment dries the skin, protect the area from the sun if you are on an oral antibiotic or a retinoid, and change into dry, breathable clothing.
If breakouts continue despite a sensible routine, the diagnosis is worth revisiting rather than adding more products.
What decides the cost of back acne treatment?
The fee depends on the diagnosis and severity, the areas covered (back, chest, shoulders), the medicines and follow-up reviews the plan needs, and whether laser or energy-based treatment is added later for marks or scars. A written quote is given at consultation, after examination and any simple tests to tell acne from fungal folliculitis. The consultation also decides whether treatment is advised at all, or whether another diagnosis needs managing first. How quotes work at this practice is explained on how we quote.
How Dr Sin Yong approaches back acne
Dr Sin Yong, an aesthetic physician, examines and plans treatment himself. The first visit is about the diagnosis, not a product: he looks at the lesions across the back, chest and shoulders, swabs or scrapes where the picture is unclear, and grades severity zone by zone. The plan follows the biology, it is set out in writing with the fee factors, and it includes the option of no treatment.
The back is harder to reach and to treat at home. Illustrative image, not a patient.
“Half of stubborn bacne is not acne. Treat the wrong diagnosis and even well-chosen products will fail.”
Dr Sin YongOn back acne
His order does not change: active disease is controlled before any laser or scar work, in the same sequence as facial acne treatment, and marks and scars are judged once the skin is quiet. Severe, scarring or treatment-resistant disease, or lesions of uncertain diagnosis, are referred for dermatology review.
Red pimples and healing marks across the upper back. Illustrative video, not a patient.
Back acne treatment: questions patients ask
Most treatments need 8 to 12 weeks to show a clear change.
Treatment depends on the type. Bacterial acne responds to benzoyl peroxide washes, topical treatments and sometimes oral medicine; fungal acne needs antifungals; and scarring or persistent acne may need laser. A doctor’s examination tells them apart.
Yes. A polyclinic or GP can manage mild to moderate acne and refer you if needed. If acne is scarring, painful or not improving after a few months, see a doctor who treats acne and scars regularly.
Korean routines focus on gentle exfoliating body washes with salicylic acid, showering soon after sweating, light non-comedogenic moisturisers and clinic treatments such as peels and lasers. The same principles work in Singapore’s humid climate.
Acne often peaks in the mid to late teens, but adult acne in the 20s and 30s is common, especially in women, and back acne can persist longer than facial acne.
Most people see fewer new spots within several weeks once oil, blocked pores and inflammation are being treated together. Dark marks fade more slowly, and deep cysts may leave scars that need separate treatment. Results vary from person to person.
The skin on the back is thicker, has larger oil glands and is covered by clothing, so sweat and friction play a bigger part. Spots there tend to be deeper and slower to heal, and are more likely to leave marks.
A family history of acne raises the risk. High-glycaemic foods and whey protein supplements have been linked with flares in some people. Diet alone rarely clears back acne, but it is reviewed as part of the history.
Zaenglein AL, Pathy AL, Schlosser BJ, et al. Guidelines of care for the management of acne vulgaris. J Am Acad Dermatol 2016;74(5):945-73.e33. PubMed
Davis EC, Callender VD. Postinflammatory hyperpigmentation: a review of the epidemiology, clinical features, and treatment options in skin of color. J Clin Aesthet Dermatol 2010;3(7):20-31. PubMed
Daniele SG, et al. Truncal acne and scarring: a comprehensive review of current medical and cosmetic approaches to treatment and patient management. American Journal of Clinical Dermatology, 2023. doi.org
Tan J, Chavda R, Baldwin H, Dreno B. Management of Acne Vulgaris With Trifarotene. Journal of Cutaneous Medicine and Surgery, 2023. doi.org
Medically reviewed by Dr Sin Yong · Updated 23 October 2026
Where Dr Sin Yong consults: 9 Scotts Road, Pacific Plaza #12-01, Singapore 228210 · Orchard MRT · Mon–Fri 10am–8pm, Sat 11am–3pm · WhatsApp +65 8023 7170 · Getting here · How fees are quoted
Back & Body Acne Consultation with Dr Sin Yong
Start with a message, not an appointment. Describe your concern on WhatsApp and you will get a straightforward reply about whether an assessment makes sense, before you commit to coming in.