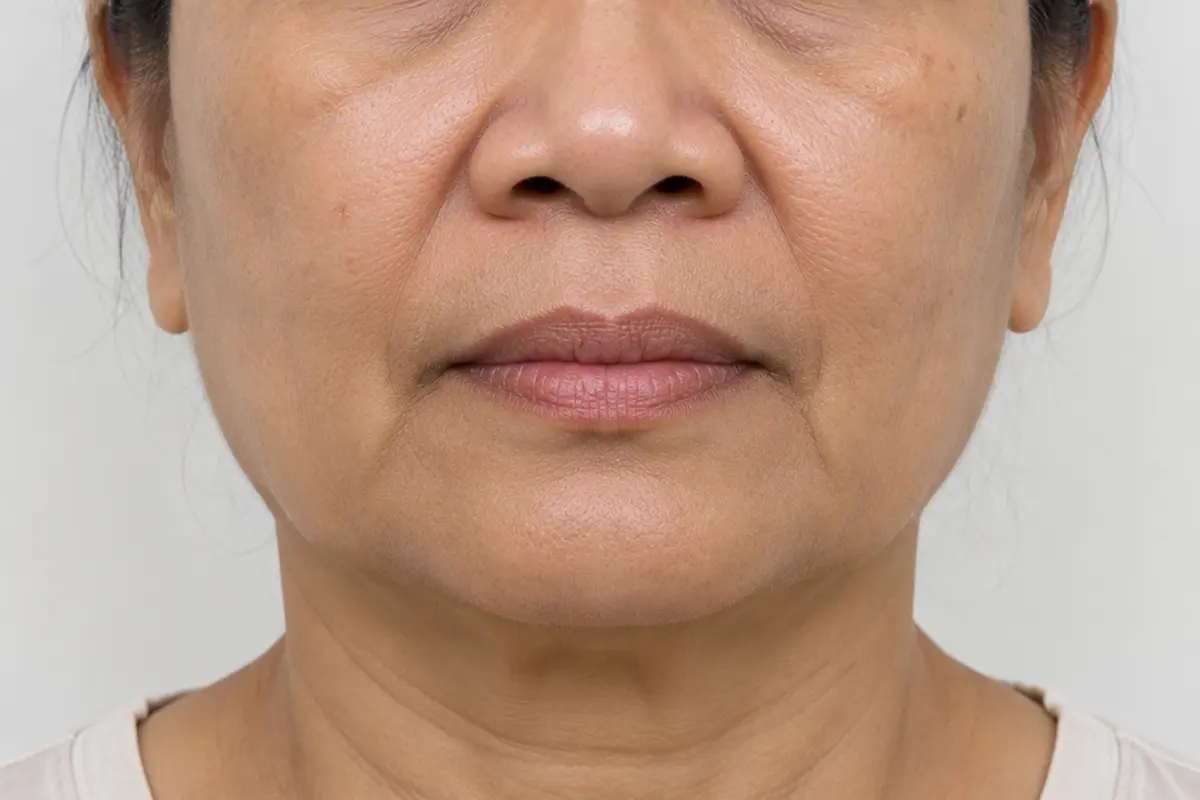
Double chin removal in Singapore: the short answer
A double chin is fat, loose skin or chin structure, and each is treated differently, so double chin removal in Singapore starts with the cause. Dr Sin Yong examines which it is, then chooses between fat reduction, Time Freeze Laser LCLR® lifting with loose-fat reduction, and tightening, without surgery.
Dr Sin Yong · MBBS (NUS) · MRCS (Edin) · MSc Aesthetic Medicine with Distinction (Queen Mary, London) · MSc Practical Dermatology (Cardiff) · Global Key Opinion Leader
Submental fullness is not one problem. It can be fat, skin laxity, the position of the platysma, or the underlying jaw and chin structure — and the four look similar from outside while responding to entirely different approaches.
Singapore's advertising rules do not allow before-and-after photos on a clinic website, so they are not shown here. Tap the button and a WhatsApp message to the clinic opens with the request already written. Send it and the team will reply with the Time Freeze Laser LCLR® before-and-after PDF.
WhatsApp +65 8023 7170 · replies within clinic hours · results vary and are assessed in person
In brief
Double chin removal in Singapore starts with what the fullness is: fat, loose skin, a low-lying platysma or a short chin. Dr Sin Yong examines the cause first, because removing fat beneath loose skin can look worse. For compact fat and laxity he uses Time Freeze Laser LCLR® or the VF Lift – Vertical Facelift. He was previously involved in chin and face liposuction cases as part of a surgical team. Today, for many patients, Time Freeze Laser LCLR® gives comparable results without surgery, and he refers to an accredited doctor where liposuction is still the answer.
A double chin describes what you see in the mirror, not what is producing it. Under the chin there are five separate contributors. They are submental fat (the fat under the chin), lax skin and the position of the platysma muscle. A weak or recessed chin is another, because it shortens the angle between chin and neck. Less often, an enlarged or low-sitting submandibular (salivary) gland plays a part. Only the first is fat.
That distinction decides everything downstream. Reducing fat where the issue is chin projection changes very little, and fat-directed treatment beneath skin that has lost its elasticity can leave the area looking looser. Many people have more than one cause, which is why a single-device answer to a double chin is usually the wrong one. A 2016 multicentre trial of submental cryolipolysis in 60 people measured its effect as a change in fat-layer thickness on ultrasound. The evidence for fat-directed treatment is evidence about fat, not about lax skin or chin projection.
Illustrative video, not a patient.
How the causes are told apart
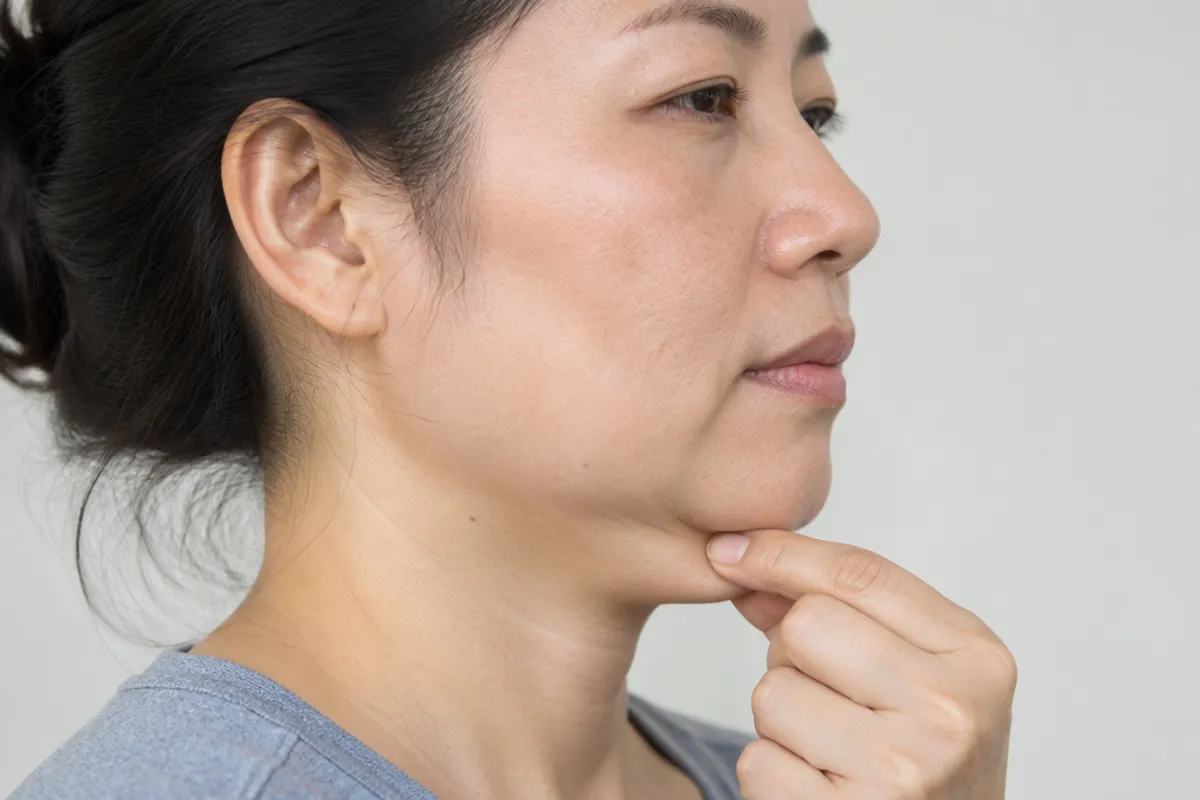
Each cause tends to reveal itself in a different way on examination. Pinching shows fat against skin, tensing the neck shows the platysma, and the profile shows the chin; the comparison below sets out what each cause responds to. New, firm or one-sided swelling in the neck is examined medically first.
A recessed or short chin is one of the most common reasons a lean person still has a double chin, and it does not respond to fat reduction at all. When the chin is set back, the line from chin to neck shortens, the angle becomes blunt, and the area reads as full in profile even when there is little fat to remove. That is why some people who lose weight see little change under the chin.
Chin enhancement with hyaluronic acid or calcium hydroxylapatite (CaHA) filler, used sparingly, addresses this structural component by projecting the chin forward. It does not remove fat or tighten skin. Hyaluronic acid can be dissolved with hyaluronidase if required; CaHA cannot, so it is placed conservatively on the bone. The chin fillers guide covers chin projection in detail.
Who double chin treatment suits, and who should wait
Suitability depends on the cause that is found and on the method being considered. The table shows how the common situations are usually handled at consultation.
Fullness in the lower cheeks has more than one cause. Illustrative image, not a patient.
Common situations found at consultation and how each is usually handled
Your situation
What usually happens
Submental fat confirmed as the driver, with skin that still recoils
Tends to suit fat-directed treatment
Loose skin under the chin and along the jawline, with little fat beneath
Tends to suit skin-directed treatment such as focused ultrasound or radiofrequency
A short or recessed chin, including in a lean person
Assessed as a chin projection question rather than fat removal
Pregnancy or breastfeeding
Better to wait
Active infection, inflamed acne or a flaring skin condition in the area
Settled first
A pacemaker or metal implants in the field (energy treatments), or a bleeding tendency or blood thinners (injections)
Reviewed before anything is planned
Marked skin excess or prominent platysma bands
Referred for a surgical opinion
A firm or growing lump, new or one-sided swelling, or an enlarged thyroid or salivary gland
Examined and referred for medical assessment, not treated cosmetically
Who should not have double chin treatment
Beyond the situations in the table, a history of reactions to filler or lidocaine, or a previous chin implant, changes the plan for chin filler. Recent filler or threads in the area are timed around. Some people's fullness comes mainly from a recessed chin, heavy skin excess or a gland. They tend to respond poorly to fat-directed treatment. Suitability is decided at consultation, not from a photograph.
Double chin removal in Singapore: the methods compared
Double chin removal in Singapore means reducing submental fat, tightening loose skin, adding chin projection, or a combination. Fat-directed methods do nothing for loose skin or a short chin, and skin-directed methods do not remove fat. The table sets the methods used here, and those given by other doctors by referral, against the cause each one is for.
In profile, fat, loose skin and a small chin can look alike. Illustrative image, not a patient.
Double chin methods compared by how they work, who they suit and who they are not for
Method
How it works
Tends to suit
Not for
Microwave fat reduction (Onda Pro Coolwaves, 2.45 GHz)
Microwave energy that is preferentially absorbed by the submental fat layer
Fullness driven mainly by fat, with reasonable skin elasticity
Does non-surgical double chin treatment work? What published studies measured
The methods have been measured separately. In the study that led to United States clearance of fat freezing under the chin, 60 people had one or two sessions. Blinded doctors correctly picked the pre-treatment photograph 91% of the time, ultrasound showed an average 2.0 mm reduction in the fat layer, and 83% of participants were satisfied. For micro-focused ultrasound, a systematic review recorded a reduction of 26 to 45 mm² in the area under the chin on side-view photographs.
Looking down makes any fullness under the chin more obvious. Illustrative image, not a patient.
Liposuction under the chin removes more, with more risk: a 2026 systematic review of 2,085 procedures found an adverse event rate of 12.9% per procedure, about three quarters of them minor. These studies treated fat. They do not show a change in loose skin or a small chin, which is why the cause of the fullness is examined first.
What double chin treatment cannot do
No single method changes fat, skin and chin structure together. Fat-directed treatment does not tighten loose skin or move the chin forward. Focused ultrasound does not shrink a full fat pad. Chin filler does not remove fat. None of them treat a gland, a thyroid swelling or an undiagnosed lump, and none replace surgery where skin excess or platysma bands are marked.
Face shape depends on bone, muscle, fat and skin. Illustrative image, not a patient.
Treatment also does not stop time: new fat can be stored if weight increases, and laxity tends to progress with age. Chin exercises have little evidence behind them, because exercising a muscle does not remove the fat lying over it. Whether skin tightens back after fat reduction is explained under skin retraction. Most double chins have two causes, and the order matters. Weight is ideally stable first, and where fat and loose skin are both present the two are treated in sequence, as set out on how to get rid of a double chin.
Is double chin treatment safe? The risks to know
Double chin treatment carries real but mostly short-lived risks, and they differ by approach.
Pinching shows how much is fat and how much is loose skin. Illustrative image, not a patient.
Microwave, radiofrequency and focused ultrasound: redness, warmth, swelling and tenderness are common. Less often there is temporary numbness or firmness under the skin and, rarely, a burn or blister where heat concentrates.
Chin filler: swelling, bruising, tenderness and lumps, and, rarely, blockage of a blood vessel. This is one reason hyaluronic acid is used and hyaluronidase is kept available.
Fat-dissolving injections: swelling, tenderness, bruising and numbness that can last for some time.
Near the jawline: energy or injections placed close to the jaw can, uncommonly, affect the nerve to the lower lip and cause temporary weakness of the smile.
These risks are reduced in four ways. The cause is established first. The treatment zone is mapped away from the jawline nerve. Settings are chosen for the tissue and skin type. Anything that does not settle is reviewed. Fat reduction beneath lax skin can also make the area look looser. This is a planning risk rather than a complication. It is avoided by checking skin recoil, meaning how well the skin springs back, at assessment.
What to expect: the assessment, the visit and aftercare
A non-surgical visit for a double chin has five steps. Each is performed or supervised by Dr Sin Yong personally at the clinic on Orchard Road, Singapore.
A set-back chin makes the neck look fuller than it is. Illustrative image, not a patient.
Assessment. The area is examined from the front and in profile, at rest and with the head tilted. Weight history, thyroid or other conditions, medicines and any earlier treatment or implant are recorded.
A plan in writing. What is producing the fullness, what each option can and cannot do, what shapes the fee, and the option of no treatment.
The treatment, matched to the cause. Energy at the fat layer where fat leads, and focused ultrasound or radiofrequency where laxity leads. Time Freeze Laser LCLR® where compact fat sits with some loss of skin quality, or chin filler where the chin is short. Where earlier filler is involved, ultrasound mapping comes first.
Straight afterwards. Warmth, redness, mild swelling or tenderness after energy treatments; bruising and swelling after injections. What to report the same day is explained before you leave.
Review. The area is reassessed as it responds, and any further step is decided then, not booked in advance.
Before you book
Declare all medicines, including blood thinners and recent steroid or hormonal treatment, but do not stop a prescribed medicine on your own.
Mention earlier injections, threads, implants or surgery in the face or neck, any thyroid condition, recent weight change, and pregnancy or breastfeeding.
Avoid strong sun beforehand, and bring photos that show the area in profile.
Expect swelling, tenderness or mild bruising; use gentle cooling if advised, and avoid pressing, massaging or applying heat to the area.
Avoid strenuous exercise and tight straps or collars under the chin if advised, and keep the skin clean and moisturised.
Use broad-spectrum sunscreen on the face and neck, and hold strong actives such as retinoids and acids until you are told to resume them.
Call the clinic for blistering or a burn-like area, a lower lip that moves unevenly, skin that turns pale or dusky, or swelling, pain or redness that is increasing.
His view is plain: you can be lean and still have a double chin, and treating fat when the cause is laxity or a short chin produces no useful change. The method is chosen once the causes are separated. Some assessments end with the advice that treatment is not needed, and some with a referral for a surgical or medical opinion.
“A weak chin and a full neck look the same in a photograph. They are not the same problem, and they do not respond to the same treatment.”
Double chin treatment in Singapore starts with the cause: fat, loose skin or chin structure. Dr Sin Yong examines which it is, then chooses between fat reduction, lifting with loose-fat reduction on Time Freeze Laser LCLR®, and tightening. Double chin reduction is planned without surgery where the cause allows it.
Non-surgical double chin treatment is usually described as warm, prickly or tight rather than painful, and the sensation depends on the device and the settings. With Time Freeze Laser LCLR® and the VF Lift – Vertical Facelift, Dr Sin Yong adjusts the energy as he works and you can ask him to pause at any point. Chin filler, where it is used, is placed with a local anaesthetic in the product or on the skin.
Often, because the two are read as one line. Loose skin along the jaw, jowls and a short chin all make fullness under the chin look heavier. Dr Sin Yong may combine the VF Lift – Vertical Facelift with Time Freeze Laser LCLR® for the jawline and neck. Where a recessed chin is part of the picture, a small amount of hyaluronic acid or calcium hydroxylapatite is placed on the chin, sparingly. The order is set at assessment.
In Singapore, medical devices, which include most aesthetic lasers, energy devices and injectable fillers, must be registered with the Health Sciences Authority (HSA) before they can be supplied. Only the lowest-risk class A devices are exempt. Ask which laser, radiofrequency, ultrasound or cooling device will be used and check it on HSA’s medical device register, and check that the clinic holds an MOH licence.
Yes. Fullness that shows when looking down at a phone or screen, but not at rest, can be posture rather than fat or loose skin. In that case it is explained rather than treated, because no device changes it. The examination is done from the front and in profile, at rest and with the head tilted, to separate posture from fat, laxity, platysma position and chin structure.
Yes. Here the VF Lift – Vertical Facelift, calibrated to reduce under the jaw, and Time Freeze Laser LCLR® are the first options for fat under the chin and loose skin. Neither injects product, so there is no filler to overfill, migrate or form lumps. Fat-dissolving injections are a prescription option given by other doctors, by referral. A short chin may still suit chin filler on bone.
Liposuction removes fat surgically; Dr Sin Yong no longer performs it, and refers to an accredited doctor where it fits. It is considered for marked fat, and a neck lift for significant laxity. Non-surgical options suit mild to moderate fat or laxity in skin that still recoils, with gradual change. Liposuction does not tighten skin that has lost its recoil or project a short chin, so the cause is confirmed first. Loose skin after earlier chin liposuction is assessed separately.
It can, if the skin was already lax. Removing fat beneath loose skin can leave it looking less supported. That is why skin recoil is checked at the same assessment. Where laxity is present, a skin-directed treatment such as focused ultrasound or radiofrequency may be planned alongside, or instead of, fat reduction.
Fullness can return if weight increases, and skin and tissue continue to age after any treatment. Fat-directed treatment does not stop new fat being stored, and laxity tends to progress over time. It is more realistic to think of results as an improvement that is maintained rather than a one-off fix.
The cost of double chin treatment in Singapore depends on the area treated, what the assessment finds, whether one approach or several is needed, and how the plan is staged. Dr Sin Yong gives a written quote at consultation after examining you, because the assessment decides whether treatment is advised at all. No figure is quoted beforehand, as it would not reflect your presentation.
A laser does not remove a large, firm fat pocket; that remains a surgical question. Where the double chin is loose fat in skin that has slackened, the Time Freeze Laser LCLR reduces that loose fat while it lifts and tightens the skin, without an incision or recovery. Whether yours is the firm or the loose kind is decided by examination at the assessment.
Safety and efficacy of cryolipolysis for non-invasive reduction of submental fat. Lasers in Surgery and Medicine, 2016. pubmed.ncbi.nlm.nih.gov
Deoxycholic acid injection: prescribing information (FDA label). U.S. Food and Drug Administration, 2015. www.accessdata.fda.gov
Ulthera System 510(k) K121700: non-invasive lift of lax tissue beneath the chin and on the neck. U.S. Food and Drug Administration, 2012. www.accessdata.fda.gov
Non-invasive system delivering microwaves energy for unwanted fat reduction and submental skin tightening: clinical evidence. Journal of Cosmetic Dermatology, 2022. pubmed.ncbi.nlm.nih.gov
Kilmer SL, Burns AJ, Zelickson BD. Safety and efficacy of cryolipolysis for non-invasive reduction of submental fat. Lasers in Surgery and Medicine, 2016. doi.org
Contini M, Hollander MHJ, Vissink A, Schepers RH, Jansma J, Schortinghuis J. A Systematic Review of the Efficacy of Microfocused Ultrasound for Facial Skin Tightening. International Journal of Environmental Research and Public Health, 2023. doi.org
Girão YRG, Soares AC, Costa FWG, Nogueira AS, Vasconcelos ACU. Adverse Events Related to Submental Aesthetic Liposuction: A Systematic Review. Journal of Oral and Maxillofacial Surgery, 2026. doi.org
Medically reviewed by Dr Sin Yong, MBBS (NUS), MRCS (Edinburgh) · Last reviewed 8 November 2026 · Editorial policy
Where Dr Sin Yong consults: 9 Scotts Road, Pacific Plaza #12-01, Singapore 228210 · Orchard MRT · Mon–Fri 10am–8pm, Sat 11am–3pm · WhatsApp +65 8023 7170 · Getting here · How fees are quoted