Pigmentation assessment at Dr Sin Yong's clinic, Orchard Road, Singapore
Pigmentation · Diagnosis Before Device · Orchard Road, Singapore

Melasma Treatment Singapore

Medically reviewed by Dr Sin Yong · Last reviewed · Doctor-performed, never delegated · Jump to questions

Melasma treatment in Singapore: the short answer

Melasma treatment in Singapore starts with diagnosis under the lamp, then strict sun discipline and topicals, then low-energy pico laser in spaced sessions to avoid rebound darkening. Dr Sin Yong explains why melasma is managed rather than removed, and how to keep it quiet.

Aftercare  Day-by-day aftercare, what to avoid and when to call

Dr Sin Yong · MBBS (NUS) · MRCS (Edin) · MSc Aesthetic Medicine with Distinction (Queen Mary, London) · MSc Practical Dermatology (Cardiff) · Global Key Opinion Leader

The two commonest pigmentation problems in Singapore look alike — and are treated almost oppositely. Getting the diagnosis right matters more than the technology.

Doctor-ledEvery assessment by Dr Sin Yong
MBBS · MRCS · MSc ×2NUS · Edinburgh · London · Cardiff
Orchard RoadBy appointment
Melasma treatment in Singapore · Dr Sin Yong, Orchard Road

Melasma is not a sun spot.
Strong lasers make it worse.

Melasma Treatment Singapore: A woman examining her cheek in a round mirror by a window (illustrative image, not a patient)
Illustrative, not a patient. Every treatment is performed by Dr Sin Yong after an in-person assessment.

Melasma sits in hormone-sensitive skin and rebounds when hit hard. Dr Sin Yong confirms the diagnosis with a lamp, starts topical treatment and sun discipline, and uses low-energy pico laser in careful sessions rather than one aggressive one.

it is melasmaConfirm

Sun spots, Hori's naevus and post-inflammatory marks mimic it and are treated differently.

the skin firstSettle

Topical lightening and strict sun protection come before any laser.

gentlyTreat

Low-fluence pico laser in spaced sessions, reviewed for rebound each time.

Suitability is decided at an in-person assessment. No prices are quoted on this page; fees are given in writing after the assessment. Images and video are illustrative, not patients.

Melasma treatment in Singapore starts with diagnosis, because melasma is a hormonal, chronic, relapsing and heat-sensitive pigmentation that is managed very differently from sun spots (solar lentigines). Dr Sin Yong separates the two at assessment before choosing any device, since an approach suited to one can aggravate the other.

Also called: chloasma, mask of pregnancy, 黄褐斑, 肝斑

Melasma Is Not Sun Spots

Melasma treatment suits patches confirmed as melasma at assessment, and Dr Sin Yong separates melasma from sun spots before any device is chosen. Many patients arrive having already had laser for what they were told was pigmentation; whether that was the right call depends entirely on which pigmentation it was.

Sun spots — solar lentigines — are deposits. They sit where UV has accumulated over years, they have defined borders, and they behave relatively predictably.

Melasma is a different condition altogether. It is hormonal, chronic and relapsing, it is driven by melanocytes that are overactive rather than more numerous, and it is heat-sensitive. It distributes in the centrofacial, malar and mandibular patterns rather than as discrete spots.

The two can coexist on the same face, which is precisely why the assessment separates them before any device is chosen. Other pigmentation types and post-inflammatory hyperpigmentation are separated at the same time.

“Melasma is managed, not cured. A clinic promising a cure is promising a relapse.”

Dr Sin YongOn pigmentation assessment
Illustrative video — not a patient.

Why Heat Matters as Much as UV Here

Singapore sits roughly one degree north of the equator. There is no seasonal low in UV, so the exposure is year-round rather than summer-weighted — which is one reason melasma behaves differently here than it does in temperate advice written for temperate climates.

The less familiar part is heat. Infrared and visible light are triggers in their own right, independent of UV. That means a hot yoga class, a steamy walk to the MRT, a kitchen, or a sunscreen that covers UVB and UVA but not visible light can all contribute. So can a heat-generating laser applied to the wrong diagnosis.

Practical management therefore has to address heat exposure and daily photoprotection alongside whatever is done in clinic. Treatment that ignores the triggers is treating one half of the problem.

“The two commonest pigmentation problems in Singapore look alike and are treated almost oppositely.”

Dr Sin YongOn melasma and sun spots · from his Instagram explainer series
A woman applying sunscreen to her cheek in a bathroom mirror
Daily sun protection is the baseline for every pigment plan.

Who it suits, who should wait, who is referred on

Cheek with faint freckles and uneven tone (illustrative image, not a patient)
Pigment is identified by type before any laser is chosen. Illustrative image, not a patient.

Tends to suit

  • Symmetric brown-grey patches confirmed as melasma at assessment
  • Pigment that persists despite sunscreen alone
  • Patients ready to combine trigger control, daily photoprotection and topical care
  • Those who accept a staged, reviewed plan

Better to wait

  • Pregnancy or breastfeeding, when elective laser is generally deferred
  • A recent tan, active dermatitis or irritation from strong actives
  • An expectation of a one-off clearance

Referred on

  • A changing, raised or unlike patch → dermatological assessment
  • Pigmentation that is not melasma on examination → dermatology referral
Who should not have this treatment
  • Pregnancy or breastfeeding (prescription agents and elective laser generally avoided)
  • Personal or family history of blood clots or a clotting disorder (oral tranexamic acid)
  • Photosensitising medication
  • Active dermatitis, infection or irritation in the treated area
  • A recent tan or sun exposure before laser
  • Known allergy to a topical ingredient

People hoping for a one-off clearance, or unable to commit to daily photoprotection and heat avoidance, tend to respond poorly, because melasma is chronic and relapsing.

Melasma option matrix: which option for epidermal, dermal or mixed melasma

Melasma treatment in Singapore is chosen by depth as much as by diagnosis. Pigment sitting in the epidermis, in the dermis, or in both is classed at assessment with dermoscopy and a Wood's lamp. That class decides which of five options carries the plan and which only supports it. The matrix below sets out how each option is used for each depth, and, because heat is itself a melasma trigger, when a laser is more likely to worsen the patch than lighten it. It is a reading aid for the consultation, not a prescription; what is used on your face is decided in person.

A woman in her forties with an even skin tone, lit by sunlight through a sheer curtain (illustrative image, not a patient)
Illustrative image — not a patient.
Melasma options by pigment depth, and when a laser makes it worse
OptionEpidermal melasmaDermal melasmaMixed melasmaWhen laser worsens itPage
Tranexamic acid (cream; oral is prescription-only and screened for clotting risk)A core topical, because it acts on the vascular and inflammatory signalling that keeps melanocytes switched onStill used, since it targets the driver rather than the deposit, but dermal pigment responds more slowlyUsually part of the plan from the startNot a laser; it is the layer that is run before any device is consideredTranexamic acid
Hydroquinone cycles (prescription)Supervised courses with planned breaks, because it slows pigment production at the epidermisLimited reach; pigment that has dropped into the dermis is not produced thereUsed for the epidermal component, in cycles, with maintenance by gentler agents between coursesNot a laser; prolonged unsupervised use carries its own risk (ochronosis), which is why courses are cycledHydroquinone
Pico toning (low energy)A cautious adjunct for stable, well-protected melasma, not a first stepLonger wavelength reaches dermal pigment; lowest energy, larger spot, longer intervals, with a stop ruleAdjunct only, after topicals and trigger control have settled the processHigh energy, small spots, short intervals, a fresh tan, or toning the same area repeatedly: rebound darkening and pale mottled spotsPico laser for melasma
R2 Glow (long-pulsed 755 and 1064 nm, inflammation-directed)Considered where the patch flushes, stings or darkens after heat, since it calms the process rather than clearing the depositDoes not clear dermal deposit; calms the inflammation that keeps producing itOften the first in-clinic step, before any pigment-directed passAny parameters chosen to fragment pigment rather than to calm; R2 Glow is run at inflammation-directed settingsR2 Glow Laser
Sun strategy (tinted iron-oxide sunscreen, heat avoidance, indoors near windows)The baseline every other option depends onThe same; dermal melasma relapses with the same triggersThe same, for as long as the tendency lastsLaser over unprotected or recently tanned skin adds heat to a trigger-driven conditionSun and haze in Singapore

Read across the rows and one pattern stands out: the topical and sun columns carry the plan at every depth, and the two lasers are adjuncts whose place depends on whether the process is calm. That is why a device is never the first step here, and why a patch that darkens after any step is reassessed rather than treated again with more energy. Hori's naevus, which is dermal pigment often mistaken for melasma, follows a different plan; see Hori's naevus (ABNOM).

How Dr Sin Yong staggers melasma treatment

Melasma treatment at this practice is staggered on purpose: each layer of the plan is started, read at review, and only then built on. The order below is the same for every face; what differs is the pace, which follows the skin.

Wood's lamp or dermoscopy first

Before anything is prescribed, the pigment is examined in daylight-balanced and angled light and, where needed, with a dermatoscope and a Wood's lamp. This confirms that the patch is melasma rather than sun spots, post-inflammatory pigment, freckles or Hori's naevus, and classes its depth as epidermal, dermal or mixed. A patch that is changing, raised or unlike the rest is examined first and referred for dermatological assessment where needed. The diagnosis, not the request, sets the protocol.

A topical loading period

Trigger control and topical therapy are started first and given time to work before any device is considered. That usually means daily tinted, iron-oxide sunscreen and heat avoidance. It also means prescription agents chosen for the depth found, such as tranexamic acid, hydroquinone in a supervised cycle, or tretinoin, after the medical history has been reviewed. Oral tranexamic acid is considered only after screening for clotting risk. Progress is judged at a review visit rather than week by week, because pigment responds in cycles. Many patches settle enough on this layer that no laser is needed.

Low-fluence laser sequencing

Where in-clinic work is appropriate, it is added only to a stable, well-protected patch, and it is sequenced. If the face flushes, stings or darkens after heat, R2 Glow at settings aimed at inflammation comes before any pass aimed at pigment. Picosecond or 1064 nm toning, if used at all, is run at the least energy that still breaks up pigment. That means a longer wavelength, a lower fluence (energy per area), a larger spot and longer intervals, sometimes with a test area first. Toning is not run on an open-ended schedule; the plan has a defined stop point. A patch that darkens or mottles after a pass is a signal to stop and reassess, not to repeat; why that happens is explained in pigmentation worse after laser. Settings are chosen for Fitzpatrick III to V skin, and treatment is deferred over a recent tan or active irritation.

Maintenance and sun rules

Stopping hydroquinone is planned, not abrupt, with maintenance handed to gentler agents such as azelaic acid, a retinoid or tranexamic acid. Daily sun protection continues indefinitely: a tinted sunscreen for visible light, reapplied through the day, worn indoors near windows, alongside shade and cooling in a climate with no seasonal low in UV. Review checks for rebound, irritation or pale patches and reconsiders hormones and heat before anything further. A return of pigment after a hot season, a pregnancy or a change of hormonal medicine is a known pattern to be reassessed, not proof that the plan failed. How the whole plan is built is on laser toning and pico laser for melasma. Lightening creams bought online, and what HSA has found in them, are covered on laser pigmentation removal.


Melasma treatment: what network meta-analyses of trials show

Network meta-analyses compare many melasma treatments at once. One, covering 39 trials with 1,394 participants, ranked a Q-switched Nd:YAG laser combined with topical medication first, and advised weighing side effects, skin type and how long the melasma has been present. A second concluded that combination treatment outperforms any single treatment.

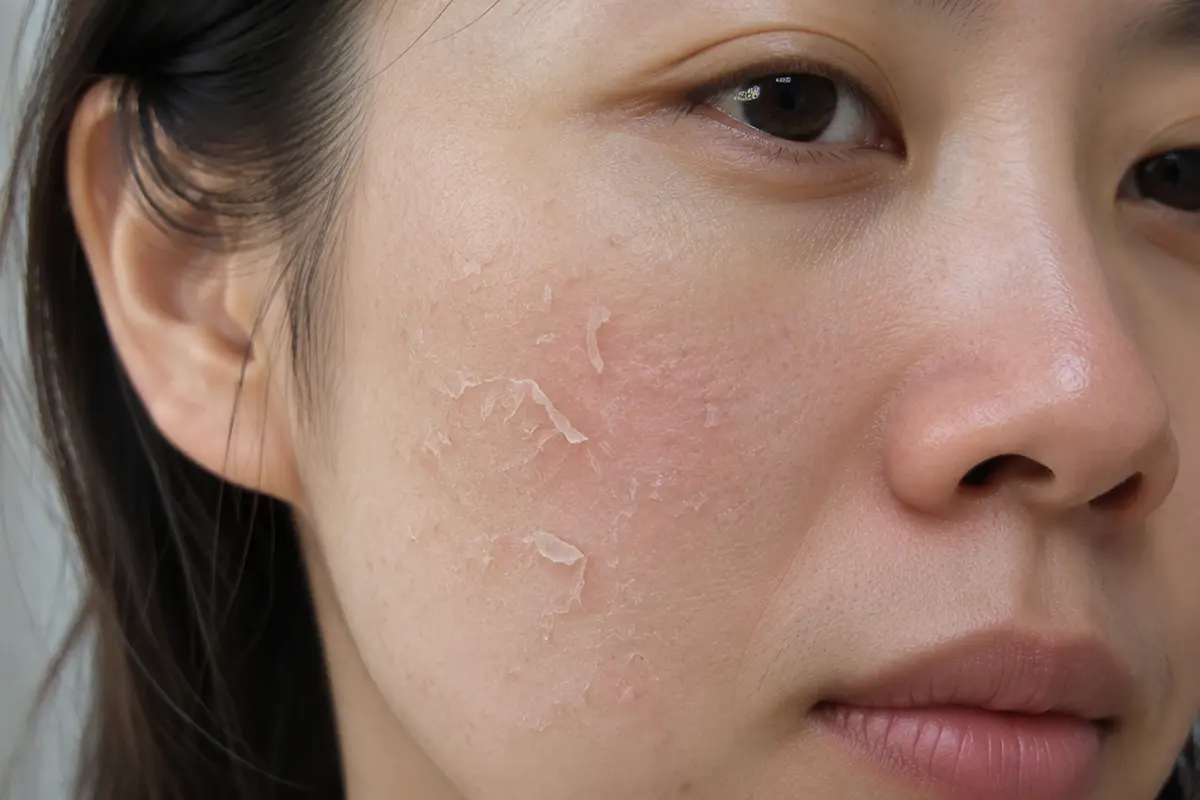
Dry skin on the cheek of a woman in her thirties (illustrative image, not a patient)
A damaged skin barrier is repaired before stronger treatments. Illustrative image, not a patient.

A 2024 meta-analysis of randomised trials found that tranexamic acid reduced melasma severity scores, most with the oral form, followed by injections and topical use. Results varied widely between studies, and side effects included stomach upset, skin irritation and menstrual changes. Tranexamic acid is a prescription medicine and is considered only after a medical consultation. Melasma tends to return, which is why treatment is staggered and maintained.

What recovery looks like after melasma treatment

The sequence below describes phases, not a timetable: how quickly each passes depends on the settings used, the area and the person, and is discussed at consultation.

Woman applying sunscreen to her cheek (illustrative image, not a patient)
Sun protection matters before and after pigment treatment. Illustrative image, not a patient.
  1. Immediately afterAfter a conservative laser pass there may be mild redness and warmth; after starting prescription creams, nothing visible at first.
  2. The first eveningSun protection is applied and reapplied from the start, because heat and ultraviolet light drive melasma more than any single treatment.
  3. The following daysPrescription creams can cause mild dryness, redness or peeling that is adjusted rather than endured; any laser redness settles.
  4. As the skin settlesPigment lightens gradually; a flare or darkening after any step is a signal to reassess the plan, not to repeat it.
  5. Follow-upReview checks for rebound, irritation or pale patches and reconsiders triggers such as hormones and heat before anything further.

The sun rules, topical schedule and rebound signs are set out in the melasma treatment aftercare guide; the Bahasa Melayu guide is melasma dan pigmentasi.

What determines the fee

The fee follows the plan, not a fixed list. It depends on what the assessment finds, since epidermal, dermal and mixed patterns are managed differently, and on the area involved, from a limited malar patch to a centrofacial distribution. It also reflects whether topical care, trigger control and in-clinic work are combined, and how the plan is staged. A written quote is given at consultation, after assessment, before anything is agreed. The consultation also decides whether treatment is advised at all.

A woman in her fifties under an umbrella in strong sun (illustrative image, not a patient)
Shade and sunscreen are the base of every pigment plan. Illustrative image, not a patient.

How quotes work at this practice: how we quote. What to declare and bring to the first visit is on the consultation process page.

In the wider picture: melasma is one of several brown marks; see pigmentation treatment and removal by type.

Melasma: sessions, downtime and how long it lasts

Melasma treatment in Singapore at a glance
How many sessionsTopical treatment for 8–12 weeks first; then 4–6 low-energy pico sessions, 3–4 weeks apart; maintenance every 2–3 months.
DowntimeNone to a day of mild redness; no peeling with low-energy settings.
How long it lastsMelasma is controlled, not cured: it returns with sun, heat and hormones unless maintenance continues.

Figures are typical ranges from Dr Sin Yong's practice and the published literature; your plan, including the number of sessions, is set after the assessment and may differ. Fees are given in writing after the assessment: see how we quote.

Why melasma returns, and a layered approach

Why melasma keeps coming back

Melasma is driven by sun and visible light, heat, hormones and genetics. Treatment lightens pigment but does not remove the tendency, so it returns when triggers continue.

A layered approach

Sun and visible-light protection every day; prescription creams; oral tranexamic acid where suitable; and gentle, low-energy laser in spaced sessions. Aggressive laser can make melasma worse.

Maintenance

After clearing, maintenance creams and occasional gentle laser keep it controlled. Summer and pregnancy can bring flares.

Melasma treatments compared

TreatmentRoleNotes
Sunscreen with visible-light protectionPrevents darkeningDaily
Prescription creamsLightens pigmentWeeks to months
Oral tranexamic acidReduces pigment activityIf suitable, after screening
Low-energy laserLightens gentlySpaced sessions

Ask about Melasma Treatment

Leave your name, mobile number and email and the clinic will contact you directly.

Your details go directly to Dr Sin Yong's clinic team and are not shared with anyone else.

Thank you — your enquiry has been received. The clinic will contact you during opening hours (Mon–Fri 10am–8pm, Sat 11am–3pm).

When to see a doctor about melasma

See a doctor if patches appeared or deepened in pregnancy or after starting hormonal medicine, if they became darker after a laser or peel, or if a lightening cream has been used for more than a few months without review.

Any spot that is new, changing in size, shape or colour, has an irregular border, itches or bleeds should be examined by a doctor before it is lasered, because a laser can hide a lesion that needed a biopsy.

Frequently Asked Questions

It can be lightened a great deal and controlled, but it tends to return, so long-term care is needed.
Combination treatment: daily sun and visible-light protection, prescription creams, oral tranexamic acid for selected patients and gentle laser. Maintenance is needed.
Korean clinics commonly use low-energy laser toning over many sessions, with brightening skincare and sun protection.
At home, daily sunscreen and topical lighteners such as azelaic acid help. Avoid harsh scrubs. Prescription creams need a doctor.
Pigment cells become overactive under the influence of sunlight and visible light, hormones such as in pregnancy or with the pill, heat and family tendency. Newer research also points to blood vessels and sun-damaged skin beneath the patch.
The evidence is supportive. A 2017 meta-analysis of 11 studies with 667 participants found tranexamic acid effective for melasma, alone or added to standard treatment, with minor side effects reported. It can be applied to the skin, injected into it or taken by mouth. Oral use is a prescription decision that needs a full medical history, because it acts on blood clotting and does not suit everyone. It does not replace sun protection.
Sometimes it fades, for example after pregnancy or after hormonal contraception is stopped, but often it persists, and sun, heat and hormonal change can bring it back. Because the tendency remains, melasma is managed rather than cured. Daily broad-spectrum sunscreen with visible-light protection, avoiding heat and reviewing triggers are the parts you control. Dr Sin Yong explains which features of your melasma are likely to settle and which need treatment.
A melasma treatment cream is chosen for the depth and history found at assessment, not by brand. A 2023 systematic review of 174 controlled trials gave the strongest recommendations to hydroquinone, triple-combination creams, sunscreens, kojic acid and azelaic acid, and strongly recommended oral tranexamic acid where there is no contraindication. Hydroquinone is used in supervised cycles because prolonged unsupervised use can cause bluish-grey discolouration.

Thermal energy is itself a melasma trigger, so a device chosen for the wrong diagnosis, or settings pushed too hard, can drive rebound hyperpigmentation. If pigmentation worsened after a session, the sensible step is reassessment before booking another rather than continuing the same approach.

Melasma is chronic and relapsing, so it is managed rather than removed. An honest plan starts conservatively, addresses heat and UV triggers, and includes daily photoprotection. Response varies between individuals and is assessed in person.

Daily photoprotection is foundational, but UVB and UVA coverage alone does not address visible light, which is also a trigger. Tinted formulations containing iron oxides are commonly used for that reason. Sunscreen is part of management rather than a treatment on its own.

Hormonal influence is well recognised, which is why melasma commonly appears or worsens in pregnancy and with hormonal contraception. That context is part of the history taken at assessment, because it shapes what is realistic to expect from treatment.

It is gradual and needs ongoing care. Aggressive or heat-based laser can darken melasma, repeated toning has been linked to pale spots, and creams can irritate or, if used unsupervised for long, cause bluish-grey discolouration. Oral tranexamic acid is not suitable where clotting risk is raised. Pigment can also return after a flare of triggers.

Yes. Melasma is less common in men, but it has the same drivers: ultraviolet and visible light, heat and an inherited tendency, and it usually sits on the cheeks, nose and forehead. It is often mistaken for sun spots or Hori’s naevus, so the examination comes first. The plan is the same as for women: sun protection, topical treatment and, where it helps, gentle low-energy laser in spaced sessions.
Laser is deferred in pregnancy, and several melasma medicines, including oral tranexamic acid and hydroquinone, are generally avoided. Daily tinted sunscreen with iron oxides, shade and avoiding heat are the mainstay, and melasma that appears in pregnancy often settles partly after delivery. Which topical, if any, is used while breastfeeding is decided case by case at consultation, and the plan is revisited once you have finished breastfeeding.
By examining the pattern, often with a Wood's lamp or dermoscope, to judge depth and to rule out look-alikes such as Hori's naevus. Treating a look-alike as melasma, or the reverse, is a common reason treatment fails.
Year-round strong UV and visible light, heat and humidity, and skin types prone to pigment all contribute.
Yes. Heat and infrared radiation can stimulate pigment cells, which is why saunas, hot yoga and cooking heat can worsen melasma.
A broad-spectrum sunscreen with iron oxides or tint, which also blocks visible light, reapplied every few hours outdoors.
Tranexamic acid is sometimes prescribed after screening for clotting risk.
Only with gentle, low-energy settings; aggressive laser can make melasma worse.
Usually two to three months to see clear improvement, then ongoing maintenance.
Yes. Pregnancy, contraceptive pills and hormone therapy can trigger or worsen it.
Retinoids and strong acids are often paused a few days before and after treatment.
Yes, heat and infrared can trigger it.

Question not answered here? Ask on WhatsApp, use the enquiry form, or browse 100 questions patients ask.

Medically reviewed by Dr Sin Yong, MBBS (NUS), MRCS (Edinburgh) · Last reviewed 8 November 2026 · Editorial policy

Speak With Dr Sin Yong

Consultations by appointment at 9 Scotts Road, Pacific Plaza #12-01, Singapore 228210.

  1. 1WhatsApp a short note on your concern
  2. 2Consultation and assessment with Dr Sin Yong
  3. 3Options explained, including no treatment

Replies within clinic hours: Mon–Fri 10am–8pm, Sat 11am–3pm · How consultations work · Prefer not to use WhatsApp? · Treatment finder · Call +65 8023 7170 · Map

WhatsApp +65 8023 7170 →

References

  1. Melasma — StatPearls / NCBI Bookshelf.
  2. Tranexamic Acid for Adults with Melasma: A Systematic Review and Meta-Analysis — BioMed Research International, 2018 / PMC.
  3. Impact of long-wavelength UVA and visible light on melanocompetent skin. Journal of Investigative Dermatology, 2010. pubmed.ncbi.nlm.nih.gov
  4. Laser therapy in the treatment of melasma: a systematic review and meta-analysis. Lasers in Medical Science, 2022. pubmed.ncbi.nlm.nih.gov
  5. Topical and Systemic Therapies in Melasma: A Systematic Review. Indian Dermatology Online Journal, 2023. pubmed.ncbi.nlm.nih.gov
  6. Efficacy and Safety of Tranexamic Acid in Melasma: A Meta-analysis and Systematic Review. 97(7):776-781. Acta Dermato-Venereologica (PMID 28374042), 2017. pubmed.ncbi.nlm.nih.gov
  7. A review of laser and light therapy in melasma. Trivedi MK, Yang FC, Cho BK. 3(1):11-20. International Journal of Women's Dermatology (PMC5418955), 2017. pubmed.ncbi.nlm.nih.gov
  8. Ma W, Gao Q, Liu J, Zhong X, Xu T, Wu Q, et al. Efficacy and safety of laser-related therapy for melasma: A systematic review and network meta-analysis. Journal of Cosmetic Dermatology, 2023. doi.org
  9. Liu Y, Wu S, Wu H, Liang X, Guo D, Zhuo F. Comparison of the Efficacy of Melasma Treatments: A Network Meta-Analysis of Randomized Controlled Trials. Frontiers in Medicine, 2021. doi.org
  10. Calacattawi R, Alshahrani M, Aleid M, Aleid F, Basamih K, Alsugair G, et al. Tranexamic acid as a therapeutic option for melasma management: meta-analysis and systematic review of randomized controlled trials. The Journal of Dermatological Treatment, 2024. doi.org
Follow Dr Sin Yong
InstagramTikTokYouTubeThreadsXLinkedInFacebook
Dr Sin Yong · Ask about pigmentation · Doctor-performed
WhatsApp Enquiry