A lump or bead in the lip, soon after filler or months later: see lip filler lumps.
Published 26 October 2026 · Reviewed by Dr Sin Yong
Lumps, filler creeping above the lip line, lips that look overfilled or uneven, swelling that returns months later, or silicone injected years ago: lip filler can go wrong in many ways, and some people are told it has to be cut out. That leaves a scar and can change the lip. Dr Sin Yong maps it with ultrasound and treats it without an incision. Get assessed first.
Short answerGet assessed before you agree to surgery. Lumps are the commonest reported problem after lip filler, and filler often does not end up where it was intended (Diwan 2023; Harris 2026). Lumps that appear years later are often granulomas, and silicone is the filler most often reported in them (Trinh, Surg J 2022). Ultrasound shows what a lump is likely made of. Hyaluronic acid is dissolved in small doses after a skin test. Silicone and other non-absorbable material, Dr Sin Yong treats with the Sculpting mode of Time Freeze Laser LCLR®, without an incision.
Lip filler gone wrong, and offered surgery? Read this first
Patients come to Dr Sin Yong after being told that lumps in the lip have to be cut out, that silicone can only be removed by an operation, or that nothing more can be done. Before you agree to surgery on your lips, know what it means:
A scar. Every cut through the skin of the face heals with a scar.
A dent. Cutting out a lump takes tissue with it, and the area can heal hollow or uneven.
Nerve injury. Nerves that give the face feeling and movement run close to where filler sits. An injured nerve can leave numbness, or weakness in a smile, a lip or a brow.
Product left behind. Filler spread through tissue is hard to remove completely.
No way back. Tissue that has been cut out cannot be put back.
The lip has its own risks. Filler that has spread through the lip and scarred it cannot simply be lifted out, so removal can mean reshaping the lip, and the edge, fullness and movement of the lip all have to heal well. The facts are set out in surgery on the lip below.
In Dr Sin Yong's practice, almost every hard lump is treated without surgery. If yours is one of the few that needs surgery, you are told plainly, and why. He maps every lump with ultrasound, dissolves hyaluronic acid, and treats silicone and other material that cannot be dissolved with the Sculpting mode of Time Freeze Laser LCLR®, without an incision.
60-second lip filler check
Not for emergencies. A change in vision or eye pain after filler: call 995 now. Difficulty breathing, a tight throat, swelling of the tongue or throat, or swelling that spreads quickly across the face: call 995 now. Pale, dusky or mottled skin, or pain that is getting worse: go now to the doctor who injected you, or to A&E. A red, hot or draining lump, or a fever: a doctor the same day; if no doctor can see you today, A&E. Do not use this check or WhatsApp for these signs.
Answer three questions and send them straight to the clinic on WhatsApp. Dr Sin Yong will let you know whether an ultrasound assessment is worthwhile. No obligation.
1 · When was it injected?
2 · What bothers you most?
3 · Have you been offered surgery for it?
Your answers open in your own WhatsApp app; nothing is stored on this page.
What goes wrong with lip filler
Most problems after lip filler fall into a few patterns, and timing is the first clue to which one you have.
Swipe sideways to see the whole table.
What you notice
When
What it usually is
What Dr Sin Yong does
Small bumps, swelling or bruising
First days, easing as the swelling settles
Expected swelling, or product that has not settled
Reviews it; no pressing or massaging unless advised
A bead or lump you can feel or see
Weeks, and it stays
Filler placed as a bolus or too close to the surface, or product that has clustered
Maps it; dissolves hyaluronic acid in small doses
A new firm, tender or swollen lump
Weeks to months later
A delayed inflammatory reaction to the filler
Treats it medically first if inflamed; the scan decides the rest
Hard lumps, sometimes in both lips
Months to years later
A granuloma, a reaction around the product; silicone is the filler most often reported
Maps it; treats what cannot be dissolved with the Sculpting mode of Time Freeze Laser LCLR®
A puffy shelf or 'moustache' above the upper lip
Months to years
Filler that has moved beyond the lip border
Maps how far it extends; dissolves the migrated part
Lips too large, the upper lip rolling outwards, or one side fuller
After several treatments
Overfilling, or filler layered over the years
Dissolves the excess in stages
Swelling that comes and goes
Months later, sometimes after an illness
A delayed reaction, sometimes set off by an infection
Treats it medically or dissolves, depending on the cause
Pale, dusky or mottled skin, or pain getting worse
Usually during or soon after the injection, sometimes later: act whenever it appears
A blocked blood vessel
Emergency: see the next section
Most complications of lip filler are mild and manageable, but blocked vessels, infection and delayed nodules can cause real problems and may need more invasive treatment (Kroumpouzos 2023). In a review of 82 published complications after lip augmentation with temporary fillers, lumps were the commonest, and migration and discoloration were also reported (Diwan 2023).
“For hard lumps from mixed products, I use one tool, Time Freeze Laser LCLR®, to target the material without surgery.”
Dr Sin YongOn hard lumps from mixed fillers and skin boosters
Vascular occlusion after lip filler: act at once
The arteries that supply the lips run inside them, close to where filler is placed. Filler that enters or presses on one of them can cut off the blood supply to part of the lip or the skin around it. The warning signs are pain that is severe or getting worse, a pale or white patch, then a dusky, purple or mottled pattern spreading across the lip or the skin above it; later, blisters or dark scabs can appear.
Urgent: a change in vision or eye pain after filler: call 995 now. Skin that turns pale, dusky or mottled, or pain that is getting worse, needs urgent assessment by the doctor who injected you, or at A&E, now. See the warning signs of a blocked blood vessel after filler.
A blocked vessel from hyaluronic acid filler is treated at once with high doses of hyaluronidase (Landau 2015), and the skin test is not done first when delay could cause harm (King 2018).
Lip filler lumps and nodules: early versus late
Lumps after lip filler are grouped by when they appear (Kroumpouzos 2023), and the timing is the first clue to the cause.
Early bumps, in the first days to weeks. Swelling, bruising or product that has not settled. Many soften as the swelling goes down. A bead that is still there after a few weeks is usually filler placed as a bolus or too close to the surface.
Delayed nodules, weeks to months later. A firm, sometimes tender lump that was not there before. In 400 patients treated with one hyaluronic acid filler in the lips or tear troughs, 4.25% had late inflammatory reactions, starting a mean of 8.4 weeks after injection, lasting up to 11 months and coming back a mean of 3.17 times; medical treatment with repeated high-dose hyaluronidase into the nodules was effective, and the authors note that rates differ between products (Artzi 2016). Across prospective studies of hyaluronic acid filler, delayed inflammatory reactions ran at about 1.1% per year (Chung 2020).
Granulomas, months to years later. A reaction around the product, often hard and sometimes in both lips. In a systematic review of 66 cases of lip nodules, they appeared a mean of 35.2 months (2.9 years) after treatment, most of those biopsied were foreign-body granulomas, and silicone was the filler most often reported, followed by hyaluronic acid (Trinh, Surg J 2022).
Some lumps are not filler at all. In a high-frequency ultrasound series, lumps that patients felt from inside the lip were the lip's own small glands, pushed forward by filler deposits, granulomas or scar tissue (Skrzypek 2021). That is one reason the scan comes before any treatment.
Swelling that comes back months after lip filler
Lips that swell again months after filler, sometimes for days at a time and sometimes more than once, usually have a delayed reaction to the filler. Late-onset reactions typically appear three to four months after injection, occasionally much sooner (Baranska-Rybak 2024). The same expert consensus lists three proposed causes: the structure of the filler, infection introduced at injection or a dormant biofilm, and the body's immune response to conditions such as a viral infection; recent dental treatment is among the risk factors.
Which treatment comes first depends on the cause. The consensus recommends hyaluronidase for non-inflammatory reactions without active infection; for an inflamed reaction, watchful waiting or medical treatment may come first, and an infection needs drainage, a culture and medical treatment rather than hyaluronidase first (Baranska-Rybak 2024). More on this pattern is in swelling months after filler.
Lip filler migration and the 'filler moustache'
Migration means filler that has ended up outside the place it was meant to sit. In the lips, the pattern people notice most is filler above the upper lip border: a puffy shelf when the lips are relaxed, a blurred lip line, or a faint 'moustache' of fullness in some lights.
Filler often does not end up in the layer intended. In an ultrasound study of 126 people, the layer under the lip skin averaged less than a millimetre, hyaluronic acid filler had ended up within the lip muscle in most of those treated, and vertical injection techniques were linked with deeper deposits and signs of migration (Harris 2026). Migration is among the lip filler complications reported in the literature (Diwan 2023). Non-absorbable gels move too: polyacrylamide gel in the lips has been found spread into the lining of the lip and the skin around the mouth years after injection (Kastner 2018).
Ultrasound shows how far the filler extends, so the enzyme can be aimed at hyaluronic acid outside the lip rather than at the whole lip. More is in lip filler migration.
Silicone and other non-absorbable filler in the lips
Liquid silicone, polyacrylamide gel and PMMA have all been injected into lips, sometimes in large volumes and sometimes by unlicensed practitioners. None of them dissolves. Reported silicone complications, such as granulomas and disfiguring nodules, usually follow large-volume injection and/or industrial-grade or adulterated material (Narins 2006). Reactions to non-absorbable fillers may appear several years after injection and show little or no tendency to improve on their own (Requena 2011), and silicone is the filler most often reported in delayed lip granulomas (Trinh, Surg J 2022).
Dr Sin Yong maps silicone and other non-absorbable fillers in the lips with ultrasound and treats them with the Sculpting mode of Time Freeze Laser LCLR®, for nodules large and small, without an incision. A lump that is red, hot or tender is treated medically first. More is in silicone filler lumps and filler done overseas.
Ultrasound first: what the scan shows in the lips
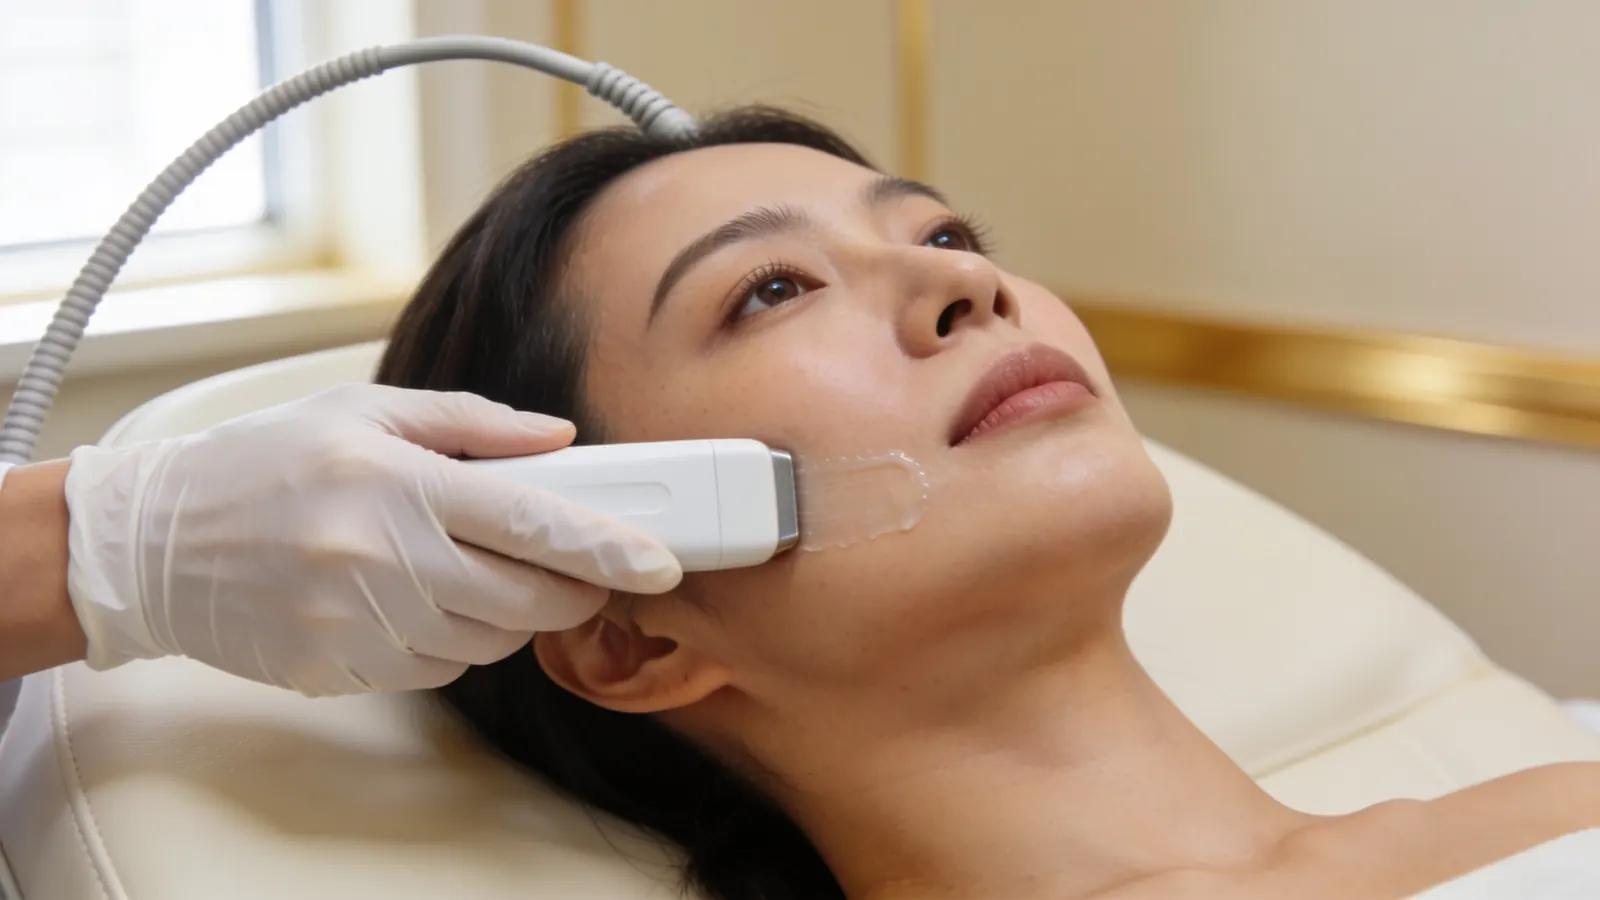
High-frequency ultrasound shows where filler sits in the lip, how deep, whether some has moved beyond the border, and what a lump is likely made of. Hyaluronic acid, silicone and other materials look different on the scan, and so do granulomas and scar tissue: in a high-frequency ultrasound series, the scan told granulomas apart from persistent filler deposits and showed fibrosis, and the authors call it essential for choosing the right treatment (Skrzypek 2021).
Illustrative image — not a patient.
A review of lip and perioral filler complications highlights ultrasound for finding and mapping filler and for watching hyaluronidase go into it in real time (Kroumpouzos 2023). Dr Sin Yong performs the scan himself, and the plan follows what it finds.
Dissolving lip filler: lumpy, overfilled or uneven lips
Most lip filler is hyaluronic acid, which can be dissolved with hyaluronidase, an enzyme that acts on hyaluronic acid only. For overcorrection or misplaced filler, a review of hyaluronidase use recommends a low dose injected directly into the palpable lump, and notes that hyaluronic acid products differ in how easily the enzyme breaks them down (Landau 2015). Dr Sin Yong dissolves lip filler in steps:
Allergy history. Reactions to bee or wasp stings, which raise the risk of allergy to the enzyme (Murray 2021), and any earlier hyaluronidase injections are asked about.
Skin test. Before planned dissolving, Dr Sin Yong always does a skin test: a small amount of hyaluronidase is injected just under the skin to check for a reaction.
A small first dose goes into the mapped lump, excess or migrated filler.
Review at about 48 hours, with any further dose titrated to what remains.
Refilling, if wanted at all, waits at least two weeks.
Overfilled lips are dissolved in stages, because dissolving more than the excess can leave the lips thinner than you want, and lips that have carried filler for years can look different once it has gone. Uneven lips are dissolved on the fuller side first and reviewed. Details are in lip filler dissolving.
Surgery on the lip to remove filler: what it involves
Removing filler from the lip means cutting into it, usually from the inside of the lip or along its edge. The lip is largely muscle, and its edge and fullness show every change, so the scar, the shape and the movement of the lip all have to heal well.
Swipe sideways to see the whole table.
Approach
What it involves
Incision
What to weigh up
Surgical removal
Cutting out filler or a granuloma, sometimes reshaping the lip
Yes
A scar; a dent or changed lip shape; numbness; product left behind; cannot be undone
Hyaluronidase
Enzyme injected into mapped hyaluronic acid
None; fine needle
Acts on hyaluronic acid only; skin test first; too much can thin the lips
Sculpting mode of Time Freeze Laser LCLR®
Laser directed at mapped material that cannot be dissolved
None
Can cause blistering or a change in skin colour, so settings are chosen for your skin
Medical treatment
Treatment for inflammation or infection
None
Comes first for a red, hot or tender lump
Waiting
Review over time
None
Reasonable for a small early bump that is settling
The published reports are plain about the difficulty. Granulomas grow finger-like into the surrounding tissue, which is why a review of treatment options puts surgical excision last (Lemperle and Gauthier-Hazan 2009). In 11 patients who had polyacrylamide gel removed from the lips, the gel had spread through all three layers of the lip with scarring in every patient, could not be drawn out with a needle, and removal meant reconstructing the lip, with fat grafting in eight. The authors judged ten of the eleven outcomes aesthetically satisfying, but one patient had severe tissue loss in the upper lip, and gel left in the lining of the lip had to be accepted (Kastner 2018).
Get assessed before you agree to an operation: it can still be done later if it is ever needed, but it cannot be undone.
Tried other treatments and almost given up?
Many patients who come to see Dr Sin Yong about lip filler problems tell him they have tried almost everything else and had given up hope. Having tried other treatments does not mean nothing more can be done: what is done next depends on what the scan shows.
That history is useful. Knowing what was injected, when, and what has already been tried often explains why a problem has stayed: hyaluronidase acts only on hyaluronic acid and only where it reaches, some fillers are not hyaluronic acid at all, and swelling or fluid can look like filler. Ultrasound helps show which of these applies, and the plan starts from there. For material that cannot be dissolved, Dr Sin Yong uses the Sculpting mode of Time Freeze Laser LCLR® for nodules large and small, without an incision. How each person responds varies.
If you have been told nothing more can be done, it is still worth having the area scanned: ultrasound helps show what is there, and the plan is made from that. Bring any records of past treatments, product names and dates if you have them. More on this is in when filler dissolving has not worked.
How Dr Sin Yong treats lip filler gone wrong
Dr Sin Yong developed the Time Freeze Laser LCLR® protocol himself and performs every scan, every dissolving injection and every Sculpting mode treatment himself on Orchard Road. He has been invited to share his clinical expertise in Seoul, Dubai, Bangkok and São Paulo, including as a Global Key Opinion Leader.
He does not add filler to hide a lump or to even out lips that are already overfilled. The problem is dealt with first and the lips are reviewed once they have settled; only then is anything else discussed, including leaving them as they are. You do not need to have been treated here, and having no records of what was injected is fine. Lumps elsewhere in the face are covered in hard lumps after filler, and the laser in the Sculpting mode of Time Freeze Laser LCLR®.
Your next step
Not for emergencies. A change in vision or eye pain after filler: call 995 now. Pale, dusky or mottled skin, or pain that is getting worse: go now to the doctor who injected you, or to A&E. Do not message or book for these signs.
1. MessageWhatsApp +65 8023 7170 with what is bothering you. A reply comes from the clinic, not a bot.
2. AssessmentDr Sin Yong examines you himself on Orchard Road, with ultrasound where earlier filler is involved.
3. A plan in writingWhat he would do, what he would not, the fee factors, and the option of no treatment.
Every treatment is performed by Dr Sin Yong personally. Singapore Medical Council registered · invited to share his clinical expertise internationally for CLASSYS, DEKA, Fotona, Hironic and Ilooda.
Usually not. Hyaluronic acid lumps are dissolved with hyaluronidase after a skin test. Silicone, polyacrylamide gel and other material that cannot be dissolved, Dr Sin Yong treats with the Sculpting mode of Time Freeze Laser LCLR®, without an incision. In his practice, almost every hard lump is treated without surgery; if yours is one of the few that needs it, you are told plainly, and why. Cutting filler out of the lip leaves a scar and can change the shape of the lip.
Many of the patients Dr Sin Yong sees have tried other treatments first. A treatment that did not help can still leave options open: hyaluronidase may not have reached the filler, the filler may not be hyaluronic acid, or what looks like filler may be swelling or fluid. Ultrasound helps show which applies, and the plan follows what it finds.
A lump in the first days is often swelling or product that has not settled. A bead that stays is usually filler placed as a bolus or too close to the surface, or product that has clustered. A new firm or tender lump weeks or months later is more often a delayed reaction, and a hard lump years later can be a granuloma (Trinh, Surg J 2022). Some lumps felt inside the lip are the lip's own glands pushed forward (Skrzypek 2021), which is one reason it is scanned.
Late lumps are usually a delayed reaction to the filler. Late-onset reactions typically appear three to four months after injection and have been linked to the filler itself, infection or biofilm, and the body's response to conditions such as a viral infection; recent dental treatment is among the risk factors (Baranska-Rybak 2024). A red, hot or tender lump is treated medically first, before any dissolving, and the scan shows what the lump is likely made of.
Nodules are firm lumps in the lip that can be felt and sometimes seen, and they are the commonest reported complication of lip filler (Diwan 2023). Some are filler that has clustered; others are an inflammatory reaction or a granuloma, a reaction around the product. In a systematic review of 66 cases, lip nodules appeared on average 2.9 years after treatment (Trinh, Surg J 2022). Ultrasound shows which kind you have, and that decides the plan.
Yes, if it is hyaluronic acid, which most lip filler is. The filler is mapped with ultrasound, Dr Sin Yong does a skin test, and a small dose of hyaluronidase goes into the lump, the excess or the migrated part, with a review at about 48 hours before any more. Silicone and other non-absorbable fillers do not dissolve; he treats them with the Sculpting mode of Time Freeze Laser LCLR®, without an incision.
Filler can spread beyond the lip border into the skin above it, leaving a puffy shelf or a faint 'moustache' when the lips are relaxed. In an ultrasound study, lip filler usually ended up within the lip muscle, and vertical injection techniques were linked with signs of migration (Harris 2026). Ultrasound shows how far it extends, and migrated hyaluronic acid is dissolved where it lies, rather than dissolving the whole lip.
Pain that is severe or getting worse, a pale or white patch on the lip or the skin around it, then a dusky, purple or mottled pattern, and later blisters or dark scabs. These need urgent assessment by the doctor who injected you, or at A&E, without waiting. A change in vision or eye pain after any filler is an emergency: call 995. Hyaluronic acid in a blocked vessel is treated at once with high doses of hyaluronidase (Landau 2015).
Silicone cannot be dissolved, and reactions to non-absorbable fillers can appear years after injection with little or no tendency to settle on their own (Requena 2011). That does not mean it has to be cut out. Dr Sin Yong maps silicone in the lips with ultrasound and treats it with the Sculpting mode of Time Freeze Laser LCLR®, without an incision. A red, hot or tender lump is treated medically first. Get assessed before you agree to surgery.
Not reliably. Massage may help a soft, early irregularity if the doctor who examined you advises it, but it does not dissolve filler, it does not move filler back from above the lip line, and it does nothing for silicone or a granuloma. Do not try to break up lumps yourself with firm pressure, heat or home devices. A bump that is still there after a few weeks is worth a scan.
Not necessarily. Some people prefer to dissolve everything and start again from their natural lips; more often the excess and the misplaced filler are dissolved and the shape that suits the face is kept. Dr Sin Yong dissolves in stages, with a review between steps, because dissolving more than the excess can leave the lips thinner than you want. New filler, if wanted at all, waits at least two weeks.
Surgery on the lip means a cut, a scar and the risk of a dent, a changed lip shape, numbness and filler left behind. In 11 patients who had polyacrylamide gel removed from the lips, removal meant reconstructing the lip; ten of the eleven outcomes were judged satisfying, but one patient had severe tissue loss in the upper lip, and gel left in the lining of the lip had to be accepted (Kastner 2018). Surgery cannot be undone, so get assessed first.
Dr Sin Yong performs the ultrasound scan, the dissolving and every Sculpting mode treatment himself, on Orchard Road. It is not delegated to another doctor, a nurse or a therapist, so the same doctor follows each lump from the first scan to the last review.
References
Evaluation of Current Literature on Complications Secondary to Lip Augmentation Following Dermal Filler Injection. Journal of Clinical and Aesthetic Dermatology, 2023. source
Complications of fillers in the lips and perioral area: Prevention, assessment, and management focusing on ultrasound guidance. Journal of Plastic, Reconstructive & Aesthetic Surgery, 2023. source
Ultrasound Evaluation of Lip Anatomy and Filler Placement: A Cross-Sectional Study of Injection Accuracy, Migration, and Demographic Variation. Plastic and Reconstructive Surgery, 2026. source
Delayed Granulomas as a Complication Secondary to Lip Augmentation with Dermal Fillers: A Systematic Review. The Surgery Journal, 2022. source
High frequency ultrasound assessment of labial glands simulating small nodules or granulomas after lip augmentation. Journal of Ultrasonography, 2021. source
Resistant and Recurrent Late Reaction to Hyaluronic Acid-Based Gel. Dermatologic Surgery, 2016. source
A Systematic Review of the Literature of Delayed Inflammatory Reactions After Hyaluronic Acid Filler Injection to Estimate the Incidence of Delayed Type Hypersensitivity Reaction. Aesthetic Surgery Journal, 2020. source
Late-Onset Reactions after Hyaluronic Acid Dermal Fillers: A Consensus Recommendation on Etiology, Prevention and Management. Dermatology and Therapy, 2024. source
Removal of Polyacrylamide Gel (Aquamid®) from the Lip as a Solution for Late-Onset Complications: Our 8-Year Experience. Aesthetic Plastic Surgery, 2018. source
Adverse reactions to injectable soft tissue fillers. Journal of the American Academy of Dermatology, 2011. source
Liquid injectable silicone: a review of its history, immunology, technical considerations, complications, and potential. Plastic and Reconstructive Surgery, 2006. source
Foreign body granulomas after all injectable dermal fillers: part 2. Treatment options. Plastic and Reconstructive Surgery, 2009. source
The Use of Hyaluronidase in Aesthetic Practice (v2.4). Journal of Clinical and Aesthetic Dermatology, 2018. source
Guideline for the Safe Use of Hyaluronidase in Aesthetic Medicine, Including Modified High-dose Protocol. Journal of Clinical and Aesthetic Dermatology, 2021. source
Hyaluronidase Caveats in Treating Filler Complications. Dermatologic Surgery, 2015. source
About this page: written and medically reviewed by Dr Sin Yong, MBBS (NUS), MRCS (Edinburgh) · Last reviewed 26 October 2026 · Illustrative images only, not patients · Editorial policy
Not for emergencies. A change in vision or eye pain after filler: call 995 now. Pale, dusky or mottled skin, or pain that is getting worse: go now to the doctor who injected you, or to A&E. Do not message or book for these signs.