Key facts
- Monolid
- No visible upper eyelid crease, often with a fuller upper lid
- Tapered crease
- Narrow at the inner corner, often tucked inside the inner fold, widening outwards
- Parallel crease
- Runs at a similar height from inner to outer corner, above the inner fold
- Hooded eyes
- Skin or brow above the crease folds down over it; the crease may still be there
- Creating or reshaping a crease
- Surgical — referred to a plastic surgery specialist
- Non-surgical lifting
- Lifts brow and periorbital support and tightens lid skin; does not form a fold
- True ptosis
- A weak lid-opening muscle; a medical finding and surgical territory
What decides whether an eyelid has a crease?
Whether an eyelid has a crease depends mainly on how the muscle that opens the eye connects to the skin. In a creased eyelid, fine fibres from the levator aponeurosis, the tendon-like sheet of the lid-opening muscle, extend forward to reach the skin; when the eye opens, the skin above that line folds inwards and a crease forms.
Anatomical studies of East Asian eyelids describe a different arrangement in many single eyelids. The orbital septum joins the levator aponeurosis lower, closer to the lashes; the fat pad behind the septum descends further down and forward in the lid; and a thicker layer of fat beneath the skin stops levator fibres reaching the skin at the usual height, so their main attachment sits nearer the lid margin. The result is a fuller upper lid with a low crease, a partly hidden crease or none at all.
None of these is a defect. A monolid, a low crease and a high crease are all normal variants, and many people have one eyelid that differs from the other. The variation matters only because it decides what any treatment can realistically change.
Monolid, tapered or parallel: what is the difference?
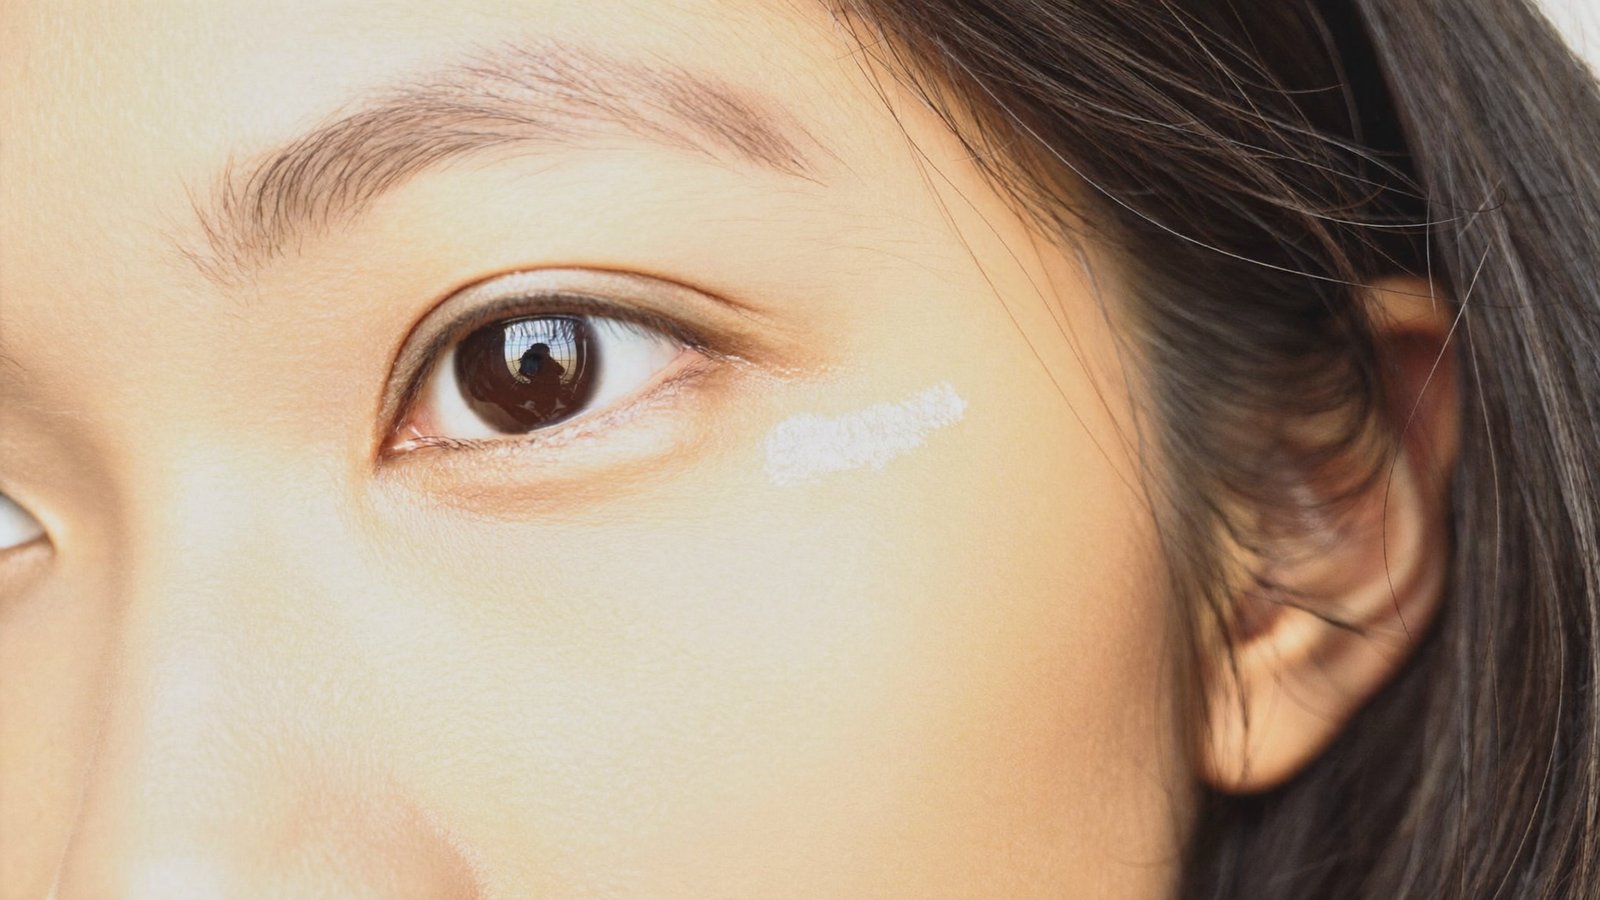
A monolid has no visible crease, a tapered crease narrows towards the inner corner, and a parallel crease runs at a similar height across the lid. These are descriptions of shape, and they are often combined with an inner fold of skin at the corner of the eye, called the epicanthal fold.
In a tapered crease the line starts narrow near the inner corner, frequently tucked inside the epicanthal fold, and widens towards the outer corner. In a parallel crease the line sits above the inner fold and keeps roughly the same distance from the lashes from one corner to the other. A crease can also be present but hidden, visible only when the lid is lifted gently or when the eye looks down. Crease height is also measured, because the same shape can sit low, at a moderate height or high above the lashes.
Hooding changes how each type appears without changing the crease itself. As skin above the crease loosens or the brow descends, a fold drapes over the lid: a tapered crease often disappears at the outer corner first, and a parallel crease can start to look narrower or uneven between the two sides. Telling a hidden crease from an absent one is the first job of the examination.
“Hooded skin and a weak eyelid muscle look alike in the mirror — they are different problems with different right answers.”
Dr Sin YongOn eyelid assessment
What does double eyelid surgery actually change?
Double eyelid surgery changes the crease itself: it creates one where there is none, raises one that is low, or reshapes a tapered line into a parallel one. It does this by fixing the skin at the planned crease line to deeper structures of the lid, so that the skin folds there when the eye opens. Dr Sin Yong does not perform eyelid surgery; it is referred to a plastic surgery specialist.
Techniques are broadly grouped into incisional, small-incision and non-incisional methods. In incisional surgery a cut is made along the planned crease, and skin, muscle or fat may be removed before the crease is fixed. Suture-based methods create the fold through small punctures without a full incision, and small-incision techniques sit between the two. The methods differ in how the crease is fixed, what tissue can be removed and how recovery runs, and the choice is made by the surgical specialist after their own examination.
Related procedures are often discussed alongside it. Upper blepharoplasty removes redundant skin, and sometimes fat, in age-related hooding. Ptosis surgery tightens or reattaches the lid-opening muscle when the lid margin itself sits low. An inner-corner procedure is sometimes added when a parallel crease is wanted and the epicanthal fold covers its start. All of these are surgery, with incisions or sutures, swelling and a recovery period set by the operating team.
What can non-surgical lifting do for hooded eyes?
Non-surgical lifting can raise and tighten the tissues that have come down over a crease, so an existing crease shows again. It suits eyelids where the crease is intact and the heaviness comes from loosened lid skin or a descending brow, which describes many people who search for double eyelid surgery from their thirties onwards.
Where the brow has dropped, energy-based lifting of the brow, temple and periorbital area is used, with focused ultrasound and radiofrequency placed at chosen depths so that the support around the eye contracts and remodels over the following weeks. BTX techniques that relax the muscles pulling the brow down can let it sit a little higher, by millimetres rather than centimetres. Where the lid skin itself is thin and crepey, fractional laser work, such as FSX Laser for mild eyelid skin laxity, is directed at tightening it, with protective eye shields in place throughout.
The aim of a non-surgical eyelid lift is to lift what holds the eyelid rather than to alter the eyelid. A tapered crease stays tapered and a parallel crease stays parallel; what changes is how much of it is covered. How much change is seen varies between individuals, and the assessment states the realistic ceiling before anything is planned.
What can non-surgical options not do?
Non-surgical options cannot create a crease, move one or change its shape. Energy devices tighten and elevate tissue; they do not form an attachment between skin and muscle, so a monolid remains a monolid, and converting a tapered crease into a parallel one or raising a low crease is a surgical goal.
They also cannot remove substantial redundant skin or fat, and they cannot repair a weak lid-opening muscle. True ptosis, in which the edge of the lid sits low over the iris even when the brow is lifted away, is a muscle and tendon problem; significant ptosis is corrected surgically, and a droop that is new, one-sided or fluctuating through the day is a medical symptom that deserves evaluation before any aesthetic discussion.
Eyelid tape and glue sit in a separate category. They create a temporary fold and can preview what a crease might look like, but the effect lasts only while the product is on, and daily traction on the thinnest skin of the body is not a long-term plan. Lids that have been taped daily for years are examined with that history in mind, because chronic traction can leave the skin looser than its age alone would explain.
How do you know which route fits your eyelids?
The route follows the anatomy found at examination, not the request made at the door. The assessment looks at whether a crease exists and at what height, how the levator muscle performs, where the lid margin and brow sit, and the quality of the lid skin; a gentle finger-lift of the brow in the mirror often shows how much of the heaviness lives above the lid rather than in it.
If the goal is a crease that is not there, or a different crease shape, the honest answer is a referral. If the crease is present and buried by hooding or brow descent, non-surgical lifting is a reasonable first step and leaves your own crease untouched. If the lid margin is low, ptosis is assessed and referred. Many eyes over forty carry a mixture of these, and the plan sequences each component on its own terms.
It is worth watching the forehead during this conversation. People with heavy lids often raise their brows all day without noticing, and the forehead lines that result are sometimes treated in isolation. Relaxing that forehead without considering the eyelids beneath can make the lids feel heavier, which is one more reason the eye area is assessed as a whole rather than feature by feature.