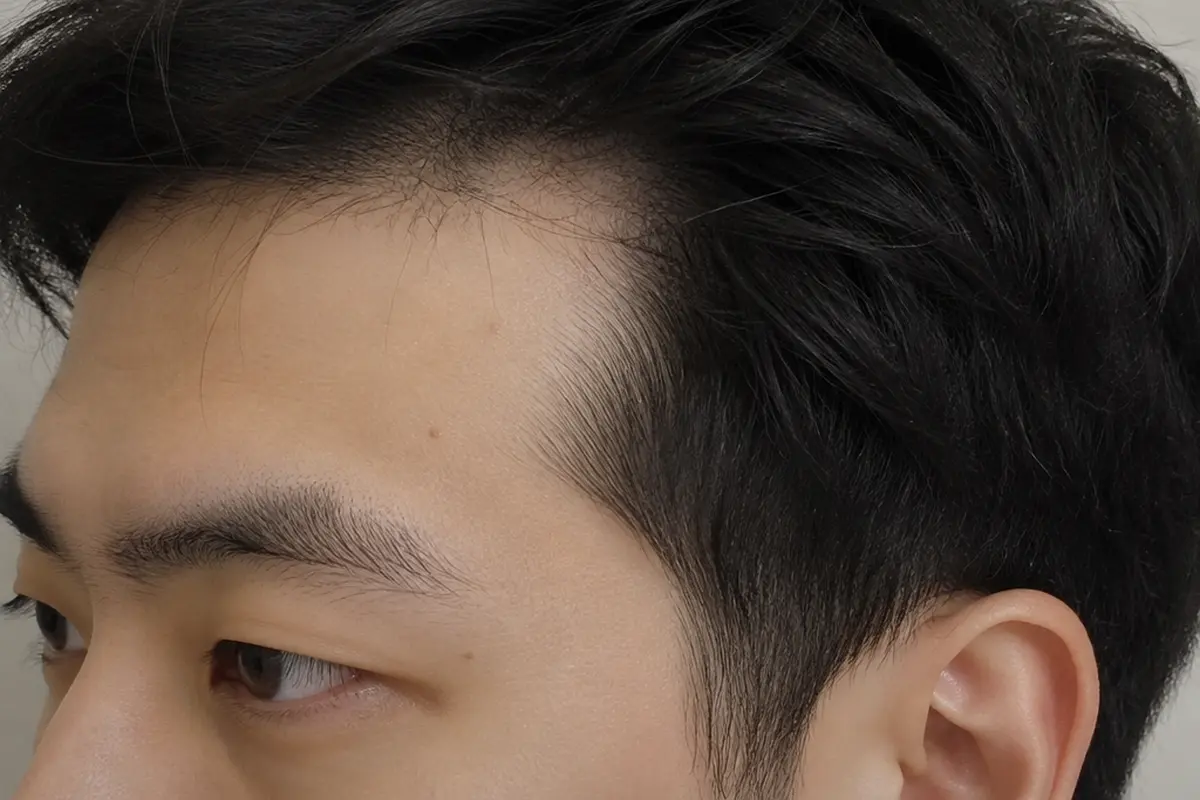A hair transplant in Singapore, as anywhere, relocates DHT-resistant follicles from the back of the scalp into bare areas by FUE or FUT, but does not stop the hair loss itself. Dr Sin Yong does not perform hair transplants. He examines the scalp, treats follicles still alive without surgery, and refers bare, stable zones to a surgical team.
A hair transplant relocates DHT-resistant follicles from the back and sides of the scalp into zones where hair has been lost; it does not stop the hair loss itself. Non-surgical restoration works on follicles that are still alive but miniaturising. The deciding question is therefore which kind of follicle you have. Bare, smooth zones with an adequate donor area are referred for a surgical opinion, while thinning zones with living follicles are usually treated medically first.
Key facts
Donor area
Back and sides of the scalp, genetically resistant to DHT — the reason relocation works
FUE
Individual follicular units harvested one at a time; small scattered dot scars
FUT
A strip of donor scalp removed and divided into grafts; a fine linear scar
What a transplant cannot do
Stop miniaturisation of the native hair around the grafts
Who performs transplants
Referred to an appropriate surgical specialist; Dr Sin Yong does not perform them
Non-surgical options here
Prescription medical therapy (educational), H2LT laser, Regenera Activa micrografting
First step
Trichoscopy, Norwood or Ludwig staging, and blood tests where indicated
Hair loss needs a transplant when follicles in a zone have gone and the donor area can spare enough to cover it. The clinical sign is a hairline or crown that has been smooth and shine-bare for some time, with no fine miniaturised hairs left to work with. No medicine, laser or injection brings back a follicle that has been lost, so in that situation relocation is the realistic tool and the patient is referred to an appropriate surgical specialist.
Most people who ask about a hair transplant are not yet in that position. Androgenetic alopecia works by miniaturisation: under the influence of dihydrotestosterone (DHT), susceptible follicles produce progressively finer, shorter hairs over successive cycles before they stop. A scalp that looks thin in photographs often still carries a large population of these miniaturising follicles, and they are exactly what medical and non-surgical treatment is aimed at.
The distinction is made by examination rather than in the mirror. Trichoscopy shows whether thinning zones still hold miniaturised hairs, and staging on the Norwood scale in men or the Ludwig scale in women describes the pattern. Blood tests look for iron, thyroid and other contributors where shedding or female thinning is involved. The answer can differ across one scalp: a bare temple and a thinning crown are not the same decision; what can be done early at the temples is covered under receding hairline.
Checking the hairline and temples: the pattern and pace of thinning decide whether a transplant is discussed. Illustrative video, not a patient.
What can non-surgical treatment do for living follicles?
Non-surgical treatment aims to slow miniaturisation and support the follicles that remain; it does not create new ones. That is a smaller promise than a transplant appears to make, but it acts on the process a transplant leaves untouched, which is why the medical side comes first in most plans.
A widening parting is a common early sign. Illustrative image, not a patient.
Prescription medicines form the foundation for pattern hair loss. Oral DHT-pathway therapy such as finasteride reduces the conversion of testosterone to DHT, and minoxidil, topical or low-dose oral, prolongs the growth phase of the hair cycle. They are described here for education only. Each needs a doctor's assessment and a discussion of side effects, such as changes in libido with finasteride or unwanted hair growth and fluid retention with oral minoxidil. Suitability is decided individually, including for women who are or may become pregnant.
Around that foundation, Dr Sin Yong's hair restoration programme uses H2LT, a calibrated laser stimulation of the scalp followed by low-level laser over the treated areas. It also uses Regenera Activa, in which small punch samples of the patient's own DHT-protected scalp are processed into a micrograft suspension and injected into thinning areas. Neither moves follicles. Both are directed at the environment of follicles still present, and response varies between individuals.
“Relocating hair does not stop the hair loss that made the transplant necessary. Restoration comes before relocation, or you are transplanting into a receding field.”
Dr Sin YongOn hair restoration sequencing
FUE or FUT: how do the two transplant methods differ?
FUE and FUT both move the same thing, DHT-resistant follicles from the donor area; they differ in how the donor hair is taken. The donor region at the back and sides of the scalp is genetically resistant to the hormone that drives pattern loss, and relocated follicles generally keep that resistance in their new position. That is the whole basis of the procedure.
Recession at the temples is the usual early sign in men. Illustrative image, not a patient.
Follicular unit excision, usually called FUE, removes individual follicular units one at a time with a small punch. It leaves tiny scattered dot scars across the donor area, which is usually clipped short for the harvest. Follicular unit transplantation, or FUT, removes a strip of donor scalp that is then divided into grafts under magnification. The wound is closed and leaves a fine linear scar that is normally covered by the hair above it.
Neither method is better in the abstract. Which suits a given scalp depends on donor density and scalp laxity, and on how many grafts are needed now and may be needed later. It also depends on whether a very short haircut matters, and on the experience of the team performing it. Both are surgical procedures with local anaesthesia, wound care and their own risks, and the decision belongs to the surgical specialist after their own examination. Dr Sin Yong does not perform either method. What DHI and the other names on a brochure refer to, and who performs each step, is set out in the guide to hair transplant cost in Singapore versus hair restoration.
Why does medical therapy matter after a transplant?
Medical therapy matters after a transplant because the transplant does not treat androgenetic alopecia. The relocated follicles resist DHT, but the native hair around and behind them remains as susceptible as before, and it keeps miniaturising unless the underlying process is managed.
Hair loss is assessed by pattern before any plan is made. Illustrative image, not a patient.
Left unmanaged, that progression changes how a transplant looks over time. Grafts placed along a hairline can end up as an isolated band in front of a crown that continues to thin, and the gap between transplanted and native hair becomes the new visible problem. Because donor follicles are finite, every graft spent chasing progression is one that cannot be used later.
This is why evidence-based guidance on androgenetic alopecia places hair transplantation alongside medical therapy rather than instead of it, and why continuing medical treatment is usually discussed as part of a transplant plan. The prescribing decision remains individual, and it is described here for education only: a doctor weighs the type of loss, medical history and side effects before anything is started or continued.
Who is not a good candidate for a hair transplant?
A transplant is a poor fit when there is no stable, well-defined zone of loss or no adequate donor supply. The commonest example is a young man with rapidly progressing loss: placing a hairline now commits limited donor hair to a pattern that may look unnatural once the loss behind it advances. Hair that is still in active retreat is usually stabilised and re-examined before anyone designs a hairline.
Diffuse thinning is another. Many women with female pattern hair loss thin across the whole crown while the frontal hairline is preserved, and the donor area may itself be thinning. That leaves little to relocate and little stable ground to relocate it to. Diffuse shedding from telogen effluvium is a different condition altogether, usually driven by a trigger such as illness, childbirth or nutritional deficiency, and it is investigated rather than operated on.
Alopecia areata is autoimmune: follicles are attacked rather than lost, and patches can regrow, so it is managed medically. Scarring alopecias, in which inflammation destroys follicles, need dermatological assessment and a period of documented stability before any surgical question arises. In each of these, the first step is a diagnosis, not a procedure.
Hair transplant side effects and risks: what the evidence shows
A hair transplant is surgery under local anaesthesia, and its side effects fall into the donor area, the recipient area and the result itself. A 2025 scoping review of 43 publications on modern hair restoration surgery concluded that serious complications are rare in the hands of experienced providers. It noted that minor complications were reported at widely varying rates and were often poorly defined (Liu 2025).
Recession at the temples is the usual early sign in men. Illustrative image, not a patient.
Donor area: bleeding, infection and persistent numbness were among the complications reported; after FUT, a widened, raised or keloid scar is possible, and over-harvesting can leave the donor area visibly thin.
Recipient area: crusting, swelling of the forehead and sterile folliculitis around the grafts were described. Temporary shedding of native hair near the grafts, often called shock loss, is another recognised effect.
The result: poor graft growth, and a hairline that looks unnatural as loss progresses behind it, leaving a band of transplanted hair in front of a thinning crown.
These are discussed and managed by the surgical team that performs the procedure, and the risk conversation belongs with them before you agree to surgery. What can be settled before that is whether surgery is the right tool at all. Is the zone bare and stable, can the donor area spare enough, and has ongoing loss been controlled? That is what Dr Sin Yong assesses, and where surgery is the answer he refers. If you have had a keloid or hypertrophic scar before, raise it, because it changes the scar risk in the donor area.
Hair transplant recovery: what the first year looks like
A hair transplant in Singapore is usually done as a day procedure under local anaesthetic, sometimes over more than one session for a large area. What follows is slow, and knowing the usual sequence helps you judge whether recovery is on track. Crusts lift over the first two weeks, most transplanted hairs shed while the follicles rest, new growth starts at around three to six months, and the result is judged at about a year. The timings are typical, not promised, and the team that performs the transplant sets the aftercare.
A widening parting is a common early sign. Illustrative image, not a patient.
Two points shape the plan here. Grafts come from the DHT-resistant donor area, but the native hair around them keeps following its own pattern, which is why medical treatment of that hair continues after a transplant. And because the result takes about a year to judge, any decision about a second session is made on the mature result, not on the early months.
How is the decision made at assessment?
The decision follows the scalp zone by zone rather than a single verdict. At assessment Dr Sin Yong examines the hairline, mid-scalp and crown with trichoscopy, stages the pattern, reviews the donor area, and asks about family history, previous treatment and how quickly change has happened. Photographs taken in standardised conditions give a baseline against which later change is judged, whichever route is chosen.
Hair loss is assessed by pattern before any plan is made. Illustrative image, not a patient.
From that, most scalps fall into one of three groups. Some have thinning with living follicles throughout, and the plan is medical and non-surgical. Some have a bare zone alongside thinning elsewhere, and the plan pairs a referral for a surgical opinion on the bare zone with medical management of the rest. A smaller group has stable, well-defined loss with an adequate donor area, where relocation is the main tool and the medical side protects the native hair around it.
Saying plainly which group you are in is the point of the consultation. A clinic that offers every scalp the same procedure, or that discusses graft numbers before anyone has looked through a trichoscope, has skipped the step that decides whether the procedure makes sense at all.
See a doctor for hair loss that is sudden, patchy, or comes with scalp pain, redness or scaling, and for shedding with tiredness, weight change or irregular periods, since these point to medical causes that are tested and treated first.
Gradual thinning at the temples, crown or parting is usually pattern hair loss, and earlier assessment leaves more follicles to work with.
How to choose a clinic for hair restoration in Singapore
A brand page or an overseas clinic cannot tell you how hair restoration is delivered here. These are the points worth checking with any clinic in Singapore.
Who performs it. Ask who will carry out hair restoration. Medical treatments here are performed by Dr Sin Yong himself and are not delegated.
What is used. Ask for the name of the device or product, and whether it is registered with the Health Sciences Authority.
Assessment first. The plan should follow an in-person assessment, not a package chosen in advance.
The fee in writing. Fees are quoted in Singapore dollars, in writing, before any treatment starts.
Review. Ask when you will be seen again after the treatment, and by whom.
Surgery. If an operation would serve you better, you should be told so and referred to a plastic surgery specialist.
Consultations with Dr Sin Yong are at 9 Scotts Road, Pacific Plaza #12-01, Singapore 228210.
Hair transplant and non-surgical hair restoration compared by what each can and cannot do
Option
What it does
What it cannot do
Typical recovery
Who it tends to suit
FUE hair transplant (referred to an appropriate surgical specialist)
Moves individual DHT-resistant follicular units from the donor area into a bare zone
Stop miniaturisation of the native hair around the grafts, or create new follicles
Small scattered dot scars in the donor area; wound care set by the surgical team
A stable, well-defined bare zone with adequate donor density, including people who wear their hair short
FUT hair transplant (referred to an appropriate surgical specialist)
Removes a strip of donor scalp that is divided into grafts for a bare zone
Stop native hair loss, or avoid a linear donor scar
A fine linear donor scar and wound care set by the surgical team
Stable loss with enough scalp laxity, where a linear scar can sit under longer hair
Prescription medical therapy (educational; needs a doctor's assessment)
Acts on the DHT pathway or the hair growth cycle to slow miniaturisation
Bring back follicles that have been lost from smooth, bare zones
Not a procedure; side effects are discussed before anything is started
Thinning zones with living follicles, and protecting native hair around a transplant
H2LT laser
Calibrated laser stimulation of the scalp followed by low-level laser over thinning areas
Move follicles or replace those already lost
A non-invasive scalp treatment with minimal recovery
Thinning zones with living follicles, alongside medical therapy
Regenera Activa
Small punch samples of DHT-protected scalp are processed into a micrograft suspension and injected into thinning areas
Move follicles, or act on zones where follicles are gone
Small punch sites at the back of the scalp, taken under local anaesthetic
Male or female pattern thinning where follicles are still present
Frequently Asked Questions
After a transplant, the moved hairs shed in the first weeks, regrow from three to four months and mature by about a year. Non-surgical treatment needs three to six months before thickening can be judged.
No. Hair transplant and hair restoration for pattern hair loss are regarded as cosmetic, so they are not covered by MediSave or most insurance plans.
Many people have one FUE procedure, and some have a second later as hair loss continues in untreated areas. The donor area is limited, so sessions cannot be repeated indefinitely. Treating the cause of ongoing loss is what protects the result.
Clinics that perform transplants usually price either per graft or as a package for a set number of grafts, with the facility and anaesthesia fees added. Quotes are comparable only when the graft count and what is included are the same. This practice does not perform transplants.
Hair transplant cost in Singapore depends mainly on the number of grafts, the method (FUE or FUT), who performs each step and the facility. It is quoted by the clinics that perform transplants. This practice does not, so no figure is given here.
An FUE hair transplant moves individual follicles from the back of the scalp to thinning areas one unit at a time, leaving small dot scars instead of a line. It relocates hair and does not stop ongoing loss, so medical treatment is usually discussed alongside it.
Transplanted follicles come from the donor area, which is genetically resistant to DHT, and they generally keep that resistance in their new position, so grafts that take usually go on growing. What changes is the hair around them: native hair keeps miniaturising unless androgenetic alopecia is managed, so the overall look can change as loss progresses. That is why a transplant plan usually includes medical care of the native hair, and why some people later consider a further procedure.
DHI is a way of placing grafts, not a different way of taking them. In both, follicular units are harvested one at a time from the donor area with a small punch. In DHI the grafts are loaded into an implanter pen that makes the opening and places the graft in one step, whereas in standard FUE the team makes the openings first and places the grafts into them. Neither name says who performs each step, which is the question worth asking.
The procedure is done under local anaesthesia, so the main discomfort is usually the anaesthetic injections, then soreness, tightness and swelling afterwards, which the surgical team manages with medication. The donor area after FUT can feel tighter than after FUE. How much discomfort you feel varies from person to person, and the surgical team explains the anaesthesia and aftercare before you agree. Dr Sin Yong does not perform transplants and refers where one is indicated.
It can rebuild a hairline where follicles at the temples have gone and the donor area can spare enough, but it does not stop the recession behind it. In a young man whose loss is still progressing, a new hairline can end up isolated in front of thinning hair. So the usual sequence is to stage the loss, treat living follicles medically and consider a transplant once the pattern is stable. Dr Sin Yong assesses this and refers where surgery fits.
Trichoscopy shows it. Fine, miniaturised hairs in a thinning zone mean living follicles that medical and non-surgical treatment can target; a smooth, shine-bare zone with no such hairs usually means follicles have been lost. Staging and blood tests complete the picture.
Some can, but many women are less suited. Female pattern hair loss is often diffuse across the crown and the donor area may thin too, leaving little stable hair to relocate. Medical assessment, including blood tests, comes first, and surgical suitability is decided by the surgical specialist.
No. Regenera Activa takes small punch samples of your own DHT-protected scalp, processes them into a micrograft suspension and injects it into thinning areas. It moves no follicles; it is directed at follicles still present, and response varies between individuals.
Androgenetic alopecia is progressive, so managing the native hair is usually an ongoing question rather than a short course. Whether a prescription medicine suits you, and for how long, is a doctor's decision after weighing your history and possible side effects. It is named here for education only.
This site does not publish fees, and Dr Sin Yong does not perform transplants; the surgical fee is set by the plastic surgery specialist or surgical team after their own examination. What decides it is the number of grafts needed, the method, the team and facility, and the follow-up included, alongside the ongoing cost of managing the native hair medically.
Hair transplants in Singapore are performed by doctors with surgical hair-restoration experience, both in public hospital plastic surgery and dermatology departments and in private clinics. Check the doctor on the Singapore Medical Council register, ask who harvests and places the grafts on the day, and ask how often the team performs the procedure. Dr Sin Yong does not perform transplants: he assesses the scalp, treats follicles that are still alive and refers stable, bare zones to a surgical team.
Transplanted hair often sheds in the first weeks, starts regrowing at about three to four months, and the result is judged at about twelve months.
Evidence-based (S3) guideline for the treatment of androgenetic alopecia in women and in men – short version. Journal of the European Academy of Dermatology and Venereology (Kanti V et al.), 2018. source
Old Friend or New Ally: A Comparison of Follicular Unit Transplantation and Follicular Unit Excision Methods in Hair Transplantation. Dermatologic Surgery (Gupta AK, Love RP, Harris JA), 2020. source
A Scoping Review on Complications in Modern Hair Transplantation: More than Just Splitting Hairs. Liu RH, Xu LJ, McCarty JC, et al. 49:585-595. Aesthetic Plastic Surgery, 2025. pubmed.ncbi.nlm.nih.gov